BPSPrep

Free lesson

Psychiatric History Components

The first lesson of BCPP Prep Course (BCPP), free to read.

Psychiatric History Components

Course: BCPP Prep Course (BCPP)

Topic: 1.1.1

Audience: Board Certified Psychiatric Pharmacist candidates

What you'll learn

  • DOMAIN: Assessment and medication-related data gathering → Subskill: Identify the psychiatric history elements that directly affect psychopharmacotherapy decisions.
  • DOMAIN: Patient-specific regimen optimization → Subskill: Separate high-yield medication history facts from distracting narrative details in board-style cases.
  • DOMAIN: Adverse effects and monitoring → Subskill: Recognize history clues that predict withdrawal, nonadherence, adverse drug reactions, and drug-interaction risk.
  • DOMAIN: Care transitions and continuity → Subskill: Build a pharmacist-ready history that supports medication reconciliation, monitoring, and handoff recommendations.
  • DOMAIN: Safety escalation → Subskill: Detect history findings that require urgent clarification, prescriber notification, or emergency referral.

Blueprint mapping

  • DOMAIN: Assessment Foundations → Psychiatric assessment elements → Medication-relevant psychiatric history collection
  • DOMAIN: Psychopharmacotherapy decision-making → Patient-specific data interpretation → Treatment selection from history clues
  • DOMAIN: Adverse-effect differentiation → Safety monitoring → Prior reactions, intolerance, and high-risk medication exposure
  • DOMAIN: Care transitions and adherence barriers → Medication reconciliation → Prior response, adherence patterns, and access barriers

Estimated time: 45–60 minutes

Prereqs: Assessment Foundations overview; course introduction. Upcoming linked topics: Mental Status Exam Findings and Screening And Monitoring Scales

Key outputs: You should be able to choose which psychiatric history details matter most for medication selection, reject attractive but low-yield distractors, and recommend what must be clarified before a psychotropic is started, continued, switched, or stopped.

Why it matters

  • Board stems often hide the correct psychopharmacotherapy answer inside the history, not the diagnosis label.
  • The safest recommendation frequently depends on one prior exposure: past response, past adverse effect, substance use pattern, pregnancy status, or adherence barrier.
  • Psychiatric pharmacists are expected to identify what must be clarified before optimizing treatment, especially when withdrawal, overdose risk, suicidality, or serious drug reactions are possible.
  • A well-structured history prevents common exam errors such as treating side effects as disease progression or restarting a previously harmful agent.

Key Terms & Must-Know Facts

Key terms

  • Chief concern: the patient-stated reason for evaluation or medication review
  • History of present illness (HPI): chronology of current symptoms, severity, triggers, and functional impact
  • Past psychiatric history: prior episodes, hospitalizations, attempts, and prior diagnoses from prior clinicians
  • Psychotropic medication history: past and current agents, doses, duration, response, and tolerability
  • Adherence history: how consistently the patient took the regimen and why doses were missed
  • Substance use history: alcohol, opioids, stimulants, cannabis, sedatives, nicotine, and withdrawal patterns
  • Family psychiatric history: psychiatric illness, suicide, bipolar disorder, and medication response in relatives
  • Social history: housing, support, work, trauma exposure, access, and legal or transportation barriers
  • Safety history: suicidality, self-harm, violence risk, overdose, access to lethal means
  • Collateral: information from family, caregivers, pharmacy fill data, charts, or outpatient team
  • Medication reconciliation: verifying what is actually being taken, not just what is listed
  • Withdrawal history: symptoms that occur when a substance or medication is reduced or stopped
  • Treatment resistance clue: failure of adequate trials rather than simple exposure to many drugs

Must-know facts

  • For exams, the most valuable psychiatric history detail is often prior medication response at an adequate dose and duration.
  • A history of mania or hypomania symptoms changes antidepressant interpretation and treatment recommendations.
  • Past serious reactions such as rash, NMS, serotonin syndrome, severe EPS, agranulocytosis, or prolonged QT require immediate clarification before restarting related therapy.
  • Substance use history is not background noise; it can explain anxiety, insomnia, psychosis, tremor, tachycardia, or poor adherence.
  • “Nonresponse” is uninterpretable without asking dose, duration, adherence, and timing of assessment.
  • Recent discontinuation of SSRIs, benzodiazepines, or antipsychotics can mimic relapse.
  • Family history of bipolar disorder, suicide, or strong medication response can influence pharmacist recommendations.
  • History must separate what was prescribed from what the patient actually took.
  • Care transition errors commonly arise from duplicate agents, omitted maintenance therapy, or undocumented PRN use.
Fig 1. Psychiatric history decision map
Exam takeaway: Use history domains to identify the single medication-relevant clue that changes the safest recommendation.
flowchart TD
A[Psychiatric history stem] --> B[Current symptom timeline]
A --> C[Past episodes and hospitalizations]
A --> D[Medication trials and response]
A --> E[Substance use and withdrawal]
A --> F[Safety and access barriers]
B --> G[Relapse vs side effect vs withdrawal]
C --> H[Bipolarity or recurrence pattern]
D --> I[Choose/reject drug based on prior response]
E --> J[Intoxication or withdrawal risk]
F --> K[Adherence and follow-up plan]

See Fig 1 for the global structure: on the BCPP exam, psychiatric history is not collected for completeness alone; it is collected to answer a medication question.

Fig 2. Medication trial interpretation flow
Exam takeaway: A prior “failed” medication trial should be rejected as evidence only if dose, duration, or adherence was inadequate.
flowchart LR
A[Prior medication listed] --> B{Adequate dose?}
B -- No --> C[Do not label true nonresponse]
B -- Yes --> D{Adequate duration?}
D -- No --> C
D -- Yes --> E{Actually taken?}
E -- No --> C
E -- Yes --> F[Interpret efficacy and tolerability]
F --> G[Reuse, augment, switch, or avoid]

See Fig 2 whenever a case claims that “several meds failed.” The exam usually wants you to test whether they truly failed.

Fig 3. Labeled psychiatric interview intake worksheet
Exam takeaway: Organize the history into symptom timeline, medication exposure, substances, safety, and social barriers to avoid missing the deciding clue.
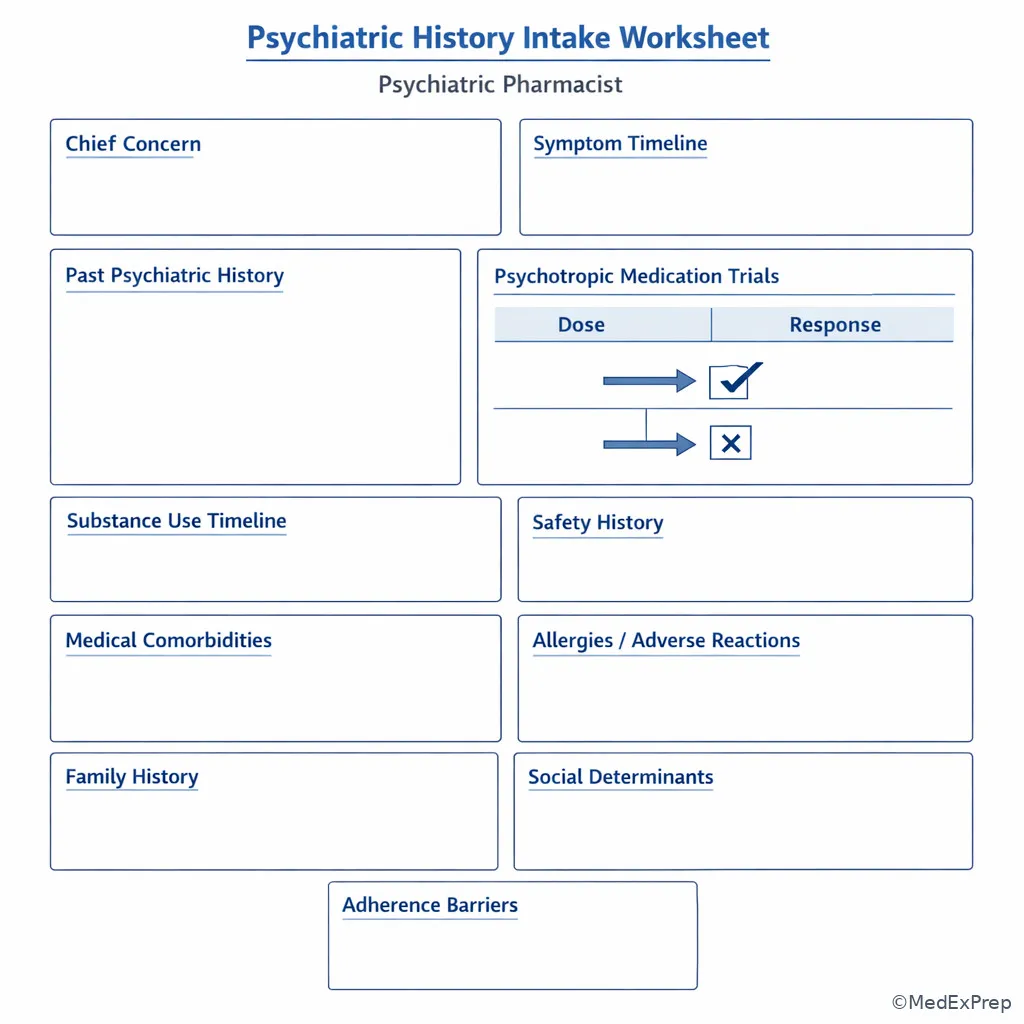
Fig 3. Labeled psychiatric interview intake worksheet

See Fig 3 as a visual checklist for what a pharmacist should verify before making a regimen recommendation.

Fig 4. Relapse versus withdrawal versus adverse effect comparison illustration
Exam takeaway: Time course and medication/substance exposure are the fastest way to distinguish disease recurrence from withdrawal or toxicity.
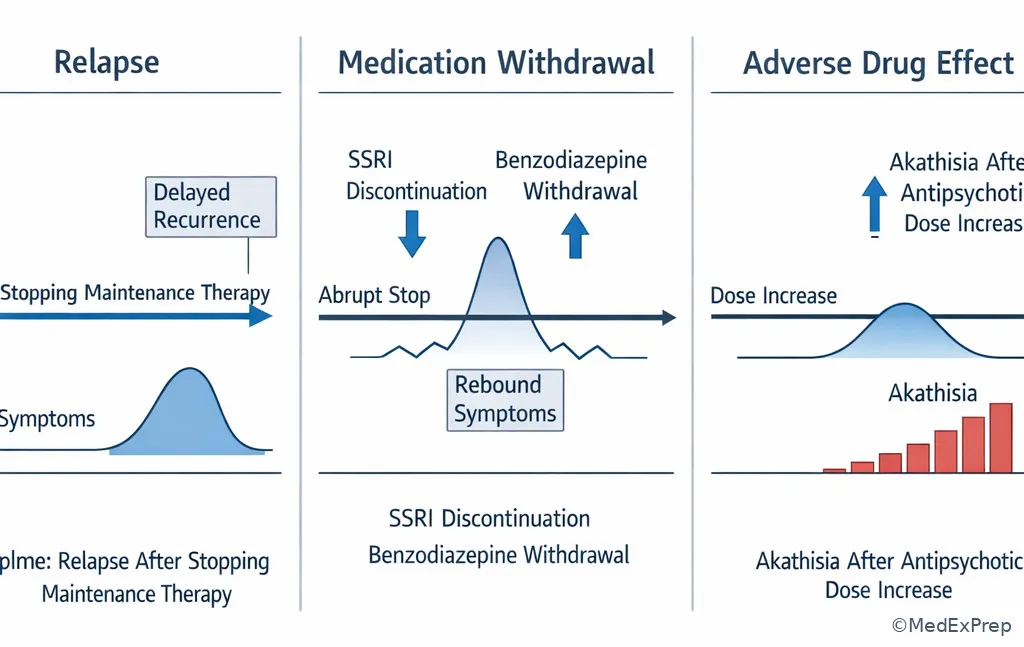
Fig 4. Relapse versus withdrawal versus adverse effect comparison illustration

See Fig 4 for one of the highest-yield stem distinctions in psychiatric pharmacy.

Fig 5. Safety escalation history algorithm
Exam takeaway: Certain history findings require immediate clarification or urgent escalation before any routine medication recommendation.
flowchart TD
A[History obtained] --> B{Active suicidality, overdose, severe withdrawal, NMS, serotonin syndrome clues?}
B -- Yes --> C[Urgent escalation / notify team / emergency protocol]
B -- No --> D{Serious prior reaction or dangerous interaction risk?}
D -- Yes --> E[Hold recommendation until clarified]
D -- No --> F{Adherence or access barrier identified?}
F -- Yes --> G[Adjust regimen and follow-up plan]
F -- No --> H[Proceed with standard optimization]

See Fig 5 for the safety-first sequence expected of the pharmacist candidate.

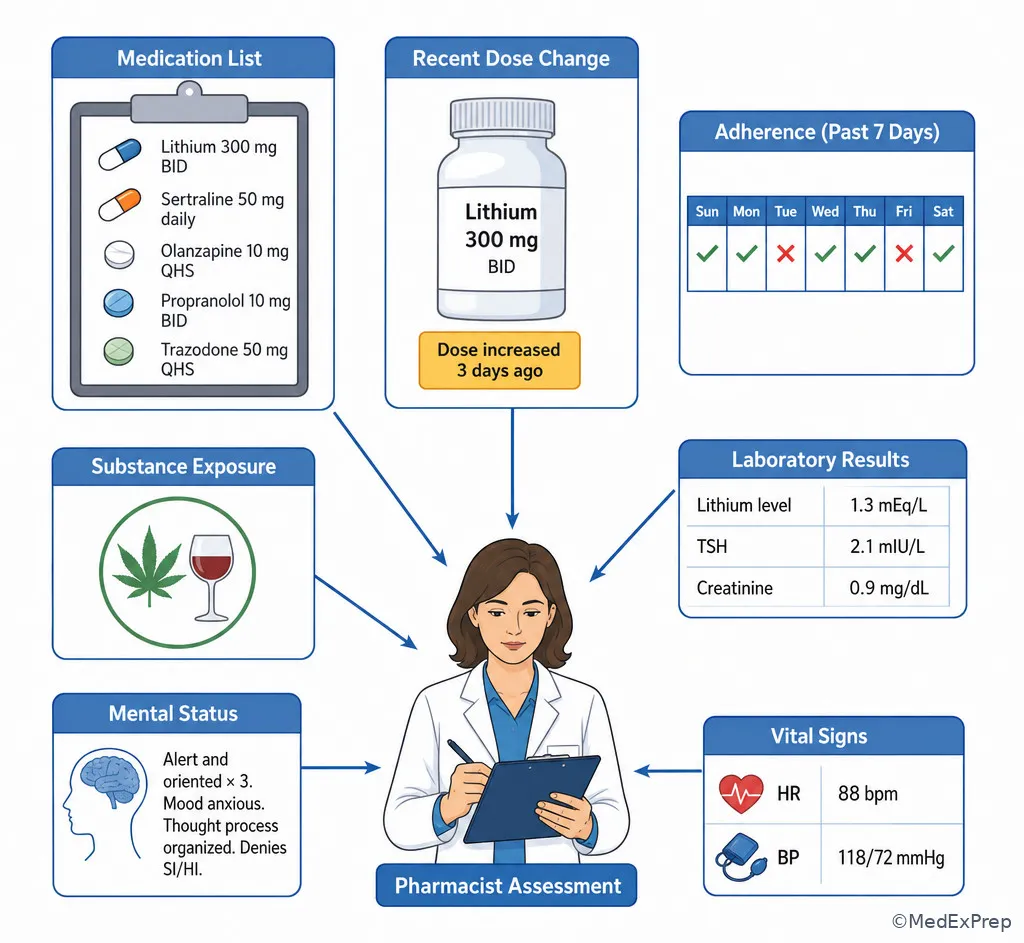
Fig 6. Pharmacist medication reconciliation in behavioral health transitions of care
Exam takeaway: The medication list, fill history, patient report, and collateral often disagree, and reconciling them changes the best next step.
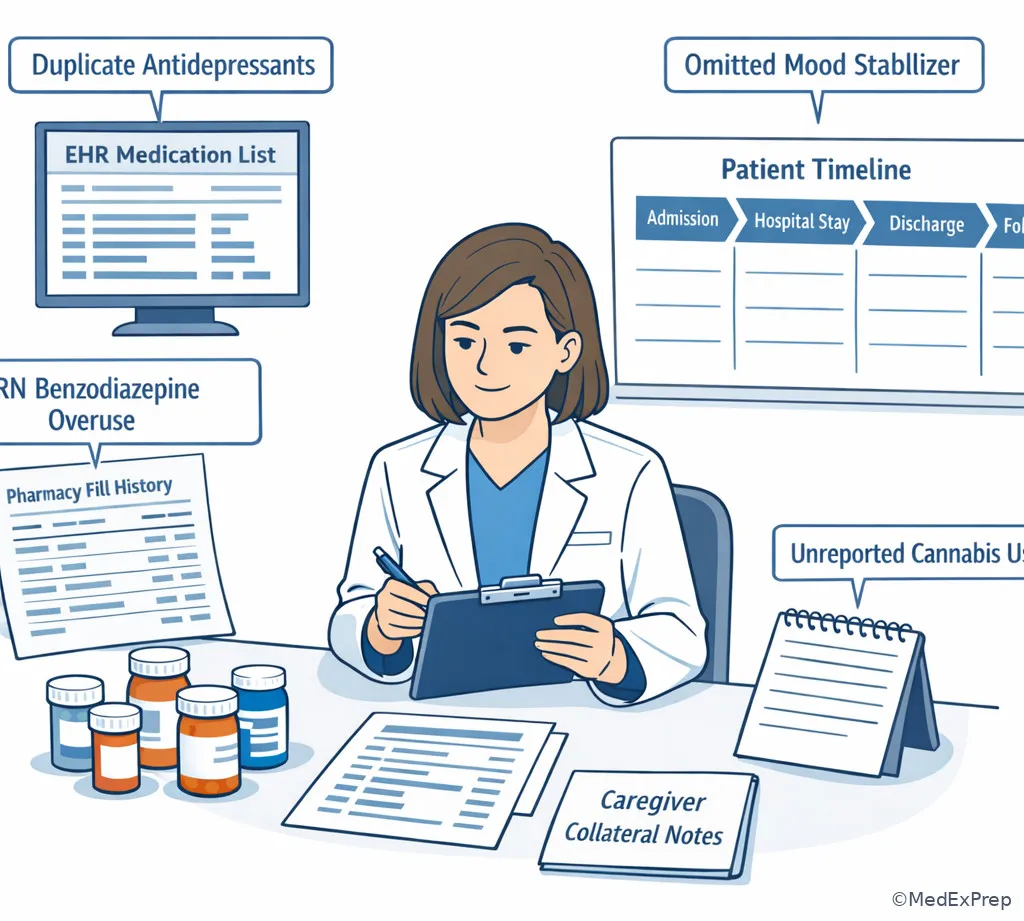
Fig 6. Pharmacist medication reconciliation in behavioral health transitions of care

See Fig 6 when thinking about inpatient admission, discharge, or urgent ambulatory follow-up.

History timeline with symptom peaks and medication changes
Exam takeaway: Plotting symptoms against dose changes is often enough to identify whether the problem is efficacy failure or drug-related harm.
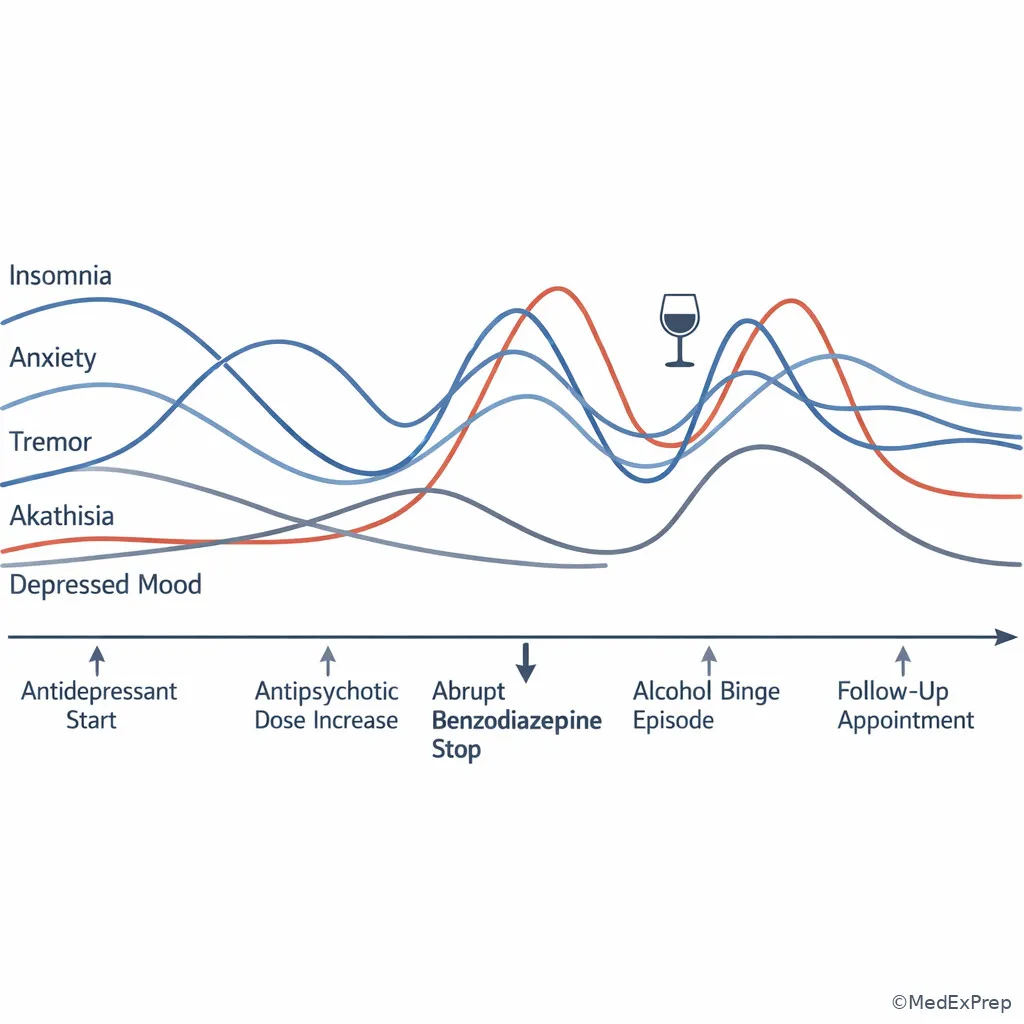
History timeline with symptom peaks and medication changes
Family history and medication response pedigree concept illustration
Exam takeaway: Family history can influence suspicion for bipolarity, suicide risk, and probable medication response patterns.
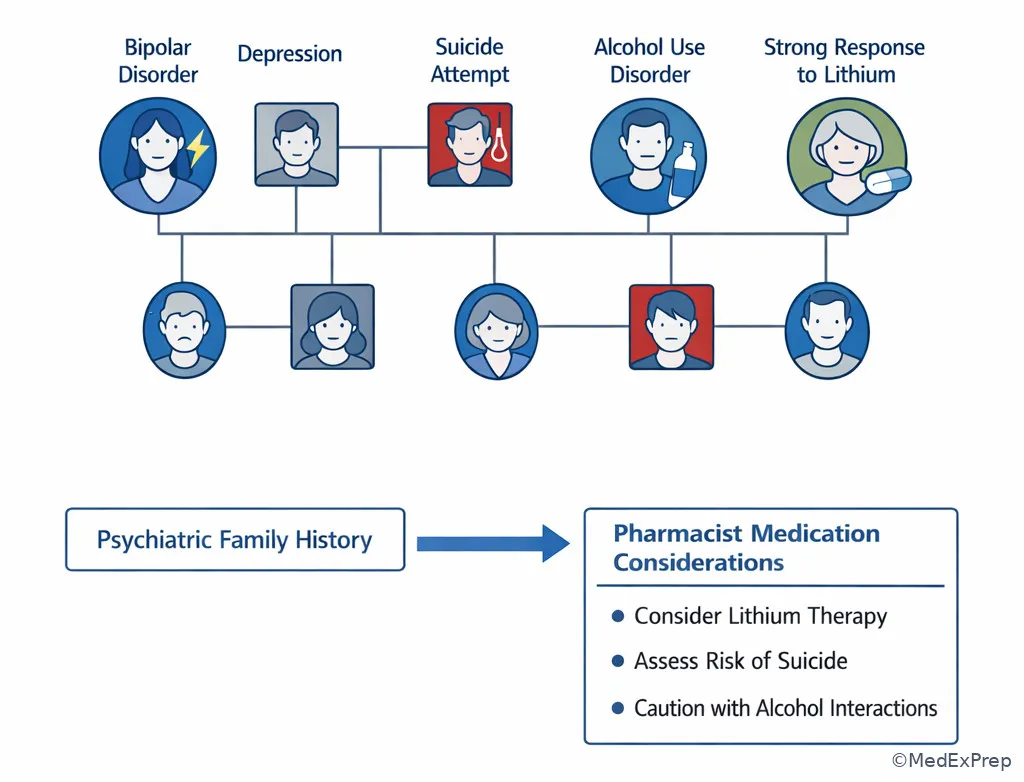
Family history and medication response pedigree concept illustration
Substance use timeline and withdrawal clues illustration
Exam takeaway: Substance type, last use, quantity, and prior withdrawal complications are more useful than a vague “uses drugs” note.
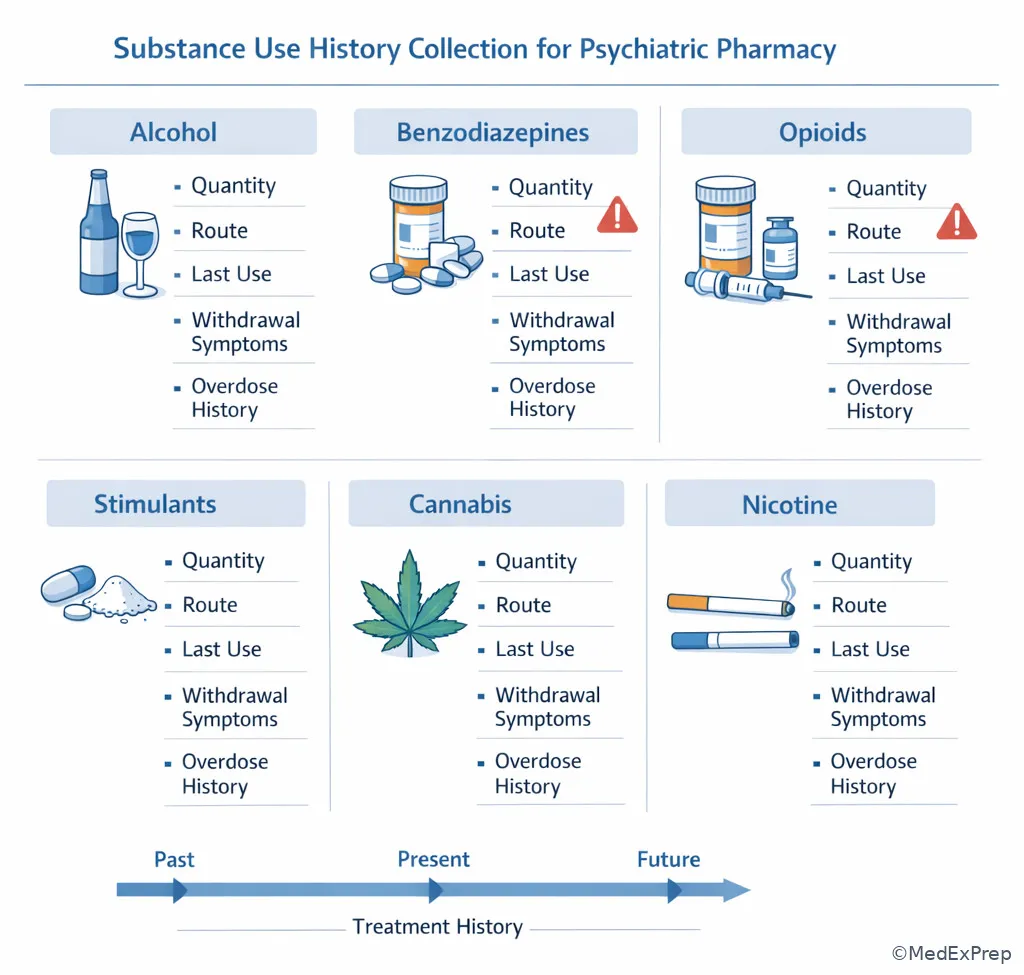
Substance use timeline and withdrawal clues illustration

Core content

1.1.1.1 Foundational structure: what belongs in a medication-relevant psychiatric history?

A. Explanation

The decision conflict is simple: which history details actually change a psychopharmacotherapy recommendation, and which details are background? The resolving rule is to prioritize domains that alter safety, efficacy, adherence, or monitoring. For the BCPP exam, a psychiatric history is not a generic interview checklist. It is a framework for deciding whether a medication should be started, resumed, avoided, clarified, or escalated.

Start with the chief concern and HPI, but interpret them through a medication lens: onset, duration, severity, functional change, recent dose changes, discontinuations, missed doses, substance use, and collateral. Then ask past psychiatric history: prior episodes, hospitalizations, suicide attempts, self-harm, violence, prior manic symptoms, psychosis, or severe withdrawal. Add medical comorbidities because they change drug choice and monitoring. Finally, close the loop with social and access history: unstable housing, inability to obtain refills, caregiver burden, transportation limits, and low health literacy can make a “failed regimen” really an implementation failure.

WHY THIS IS TESTED: exam stems commonly bury the decisive clue in the history domain most learners skip: prior hypomania before an SSRI, abrupt benzodiazepine stoppage before “panic,” or a prior dystonic reaction before antipsychotic re-exposure.

Recall: This is the first topic in the sequence, so build a baseline template now. In the upcoming topic on Mental Status Exam Findings, you will add the real-time observable findings that complement this history.
Concept flow: History domains that change medication decisions
Current problem
Define symptom timing, severity, and recent medication or substance changes.

Medication relevance
Ask whether the history changes drug choice, dose, monitoring, or safety.

Past patterns
Check prior episodes, prior responses, and prior serious reactions.

Practical barriers
Clarify adherence, access, refill history, and collateral before concluding failure.

Memory anchor: Use C-SPAMS-FS for a fast intake scaffold: Chief concern, Symptom timeline, Past episodes, Adherence, Medications, Substances, Family history, Social/safety.

B. Worked example

A 34-year-old woman with generalized anxiety disorder, migraines, and hypothyroidism presents for pharmacist-led medication review after “sertraline failure.” Her active list includes sertraline 50 mg orally daily, hydroxyzine 25 mg orally at bedtime as needed, and levothyroxine 100 mcg orally daily. She reports persistent anxiety and insomnia for 3 weeks. A distracting clue is that she also drinks two large energy drinks daily. Chart review shows sertraline was started 18 days ago after she had stopped paroxetine 40 mg/day abruptly because she ran out. The task is to recommend the most appropriate next step in medication assessment.

Reasoning chain: Identify task: determine whether sertraline truly failed. Extract key facts: low-dose early sertraline exposure, abrupt paroxetine stop, insomnia/anxiety shortly after switch, stimulant intake noise. Apply rule: no medication should be labeled ineffective before adequate duration and adherence are assessed; discontinuation symptoms from prior SSRI may mimic relapse. Eliminate distractors: increasing hydroxyzine treats symptoms but ignores the timeline; switching sertraline again is premature; declaring stimulant-induced anxiety alone misses the antidepressant transition. Verify: clarify discontinuation symptoms, adherence, refill access, and whether a more gradual cross-taper or supportive management is needed.

C. Exam trap

Common wrong answer: “Past psychiatric history” means only prior diagnoses and hospitalizations.
Why it is tempting: learners remember the interview outline but forget that psychopharmacotherapy hinges on prior drug response and adverse effects.
Single clue that eliminates it: if the stem asks for the best medication recommendation, the useful history is the part that changes treatment choice, especially prior trial quality and serious reactions.

D. Checkpoint

Question: A pharmacist reviews a referral for “multiple antidepressant failures” in a 41-year-old man taking escitalopram 10 mg orally daily for 2 weeks. Which psychiatric history detail most requires clarification before recommending augmentation?

  1. Whether his father had alcohol use disorder
  2. Whether the escitalopram trial reached an adequate dose and duration
  3. Whether he prefers evening dosing
  4. Whether he had childhood attention problems

Answer: B

  • A: Tempting because family history matters, but it is not the single most immediate discriminator for declaring antidepressant failure here.
  • B: Correct because adequacy of dose and duration determines whether augmentation is appropriate or premature.
  • C: Tempting because tolerability and adherence can depend on timing, but dose-duration adequacy is the primary unresolved rule in this stem.
  • D: Tempting because ADHD history may influence future treatment, but it does not decide whether the current antidepressant failed.
If you missed this: Review 1.1.1.1 Foundational structure: what belongs in a medication-relevant psychiatric history? — focus on the rule that a prior “failure” is uninterpretable without adequate dose and duration.
Pharmacist Action: NOTICE: vague phrases such as “failed several meds.” SAY: “Before we call this nonresponse, I need the actual dose, duration, and whether doses were missed.” MONITOR: refill history, symptom timing, and adverse effects at each transition. HOLD/CLARIFY/ESCALATE: hold any major change if the current regimen has not had an adequate trial or if abrupt discontinuation may explain symptoms.

1.1.1.2 Past psychiatric and medication history: choosing between true nonresponse, intolerance, and inadequate trial

A. Explanation

The key decision conflict is whether a prior psychotropic exposure should push you to reuse, avoid, or reinterpret a medication. The single rule is that every prior medication exposure must be sorted into one of four buckets: effective and tolerated, effective but not tolerated, ineffective despite an adequate trial, or never adequately tested. These are not equivalent, and the exam often hinges on this distinction.

For each prior agent, collect the name, dose, route, frequency, duration, adherence, benefit, onset of benefit, adverse effects, discontinuation reason, and whether discontinuation was abrupt or planned. Ask specifically about severe reactions: dystonia, akathisia, parkinsonism, tardive symptoms, serotonin syndrome, NMS, rash, neutropenia, mania induction, severe sedation, sexual dysfunction, weight gain, or QT-related events. One prior severe reaction can eliminate an otherwise attractive option.

Past psychiatric history also includes prior hospitalization, suicide attempts, ECT, long-acting injectable use, treatment court or supervised administration, and prior periods of excellent stability. Those details guide future recommendations. A patient who did well for years on one agent but stopped because of cost or transportation is different from a patient who had no benefit after multiple adequate trials.

WHY THIS IS TESTED: many stems try to make a medication look ineffective when the actual issue is short duration, low dose, poor adherence, or intolerability that could be managed rather than a true class failure.

High-Yield Connection: This concept is tested alongside Switching And Cross-Tapering Antidepressants and Maintenance Adherence Strategies. Know both the prior trial quality and the reason a drug was stopped; exams frequently pair them.
Concept flow: Interpreting a prior psychotropic trial
Verify exposure
Confirm actual drug, dose, schedule, and time on therapy.

Adequate trial?
If no, reject “true failure.” If yes, assess efficacy and tolerability separately.

Classify outcome
Helpful/tolerated, helpful/not tolerated, ineffective, or unclear due to nonadherence.

Act
Recommend reuse, mitigation, switch, augmentation, or safety avoidance.

B. Worked example

A 52-year-old man with schizophrenia, type 2 diabetes, and tobacco use disorder is admitted from an ED boarding unit. Home medications are listed as olanzapine 20 mg orally nightly, metformin 1000 mg orally twice daily, and nicotine patch 21 mg/day. A tempting wrong clue is his fasting glucose of 220 mg/dL, which may push learners away from olanzapine. His sister reports he was “doing best” on olanzapine but stopped it 3 months ago because he lost insurance and gained weight; since then he intermittently used leftover quetiapine 100 mg at bedtime. The team asks for a pharmacist recommendation on antipsychotic restart.

Reasoning chain: Identify task: choose whether prior olanzapine should be reused or rejected. Extract key facts: documented robust response on olanzapine, discontinuation due to access and metabolic burden rather than inefficacy, poor adherence after loss of insurance, partial self-treatment with subtherapeutic quetiapine. Apply rule: prior strong response is high-value evidence; if stopped for cost or adherence, consider strategies that preserve efficacy while addressing barriers. Eliminate distractors: declaring “olanzapine failure” is wrong; using the recent quetiapine exposure as evidence of antipsychotic nonresponse is wrong because the dose/pattern were inadequate; ignoring the metabolic history is also wrong because the same response must be balanced against risk. Verify: recommend restarting an antipsychotic with recognition of prior efficacy, but pair the recommendation with metabolic mitigation and access planning; if local team is considering a long-acting option, note that upcoming LAI topics build on this logic.

C. Exam trap

Common wrong answer: Counting the number of past medications as evidence of treatment resistance.
Why it is tempting: stems often list many drugs to create an illusion of refractory illness.
Single clue that eliminates it: true resistance requires adequate prior trials; a medication stopped after 5 days for nausea or taken intermittently is not equivalent to an adequate failure.

D. Checkpoint

Question: A patient reports that venlafaxine XR 75 mg orally daily “did not work,” and the prescriber asks whether this supports class failure. Which additional history best determines whether the trial was interpretable?

  1. Whether the patient took it with breakfast
  2. Whether the patient’s sibling responded to duloxetine
  3. Whether the patient remained on the dose long enough with consistent adherence
  4. Whether the patient prefers capsules to tablets

Answer: C

  • A: Tempting because administration issues can affect tolerability, but the core question is adequacy of exposure.
  • B: Tempting because family response can be clinically useful, but it does not validate this patient’s supposed nonresponse.
  • C: Correct because duration plus adherence determine whether the reported failure can guide future class selection.
  • D: Tempting because formulation preference matters for adherence, but it does not answer whether the prior trial was adequate.
If you missed this: Review 1.1.1.2 Past psychiatric and medication history: choosing between true nonresponse, intolerance, and inadequate trial — focus on the four-bucket interpretation of prior drug exposure.
Quick Recall:

  • The most useful detail in a prior medication history is prior response at an adequate dose and duration.
  • True or False: A drug stopped after severe akathisia should be documented as “nonresponse.”
  • Name the 3 minimum details that make a prior trial interpretable: dose, duration, and ______.
Pharmacist Action: NOTICE: reported “allergy” or “failure” without reaction details. SAY: “What exactly happened, after how long, and at what dose?” MONITOR: prior efficacy, onset, adverse effects, and discontinuation reason during every medication reconciliation. HOLD/CLARIFY/ESCALATE: hold class re-exposure if prior serious reaction history is unclear or if the “allergy” may represent NMS, severe rash, or hematologic toxicity.
Forward reference: In the upcoming lesson on Screening And Monitoring Scales, you will convert historical symptom severity into standardized baseline and follow-up measurements. History tells you what happened; scales help measure how much.

1.1.1.3 Substance use, withdrawal, and medical history: when the “psychiatric” complaint is not primary psychiatric worsening

A. Explanation

The decision conflict here is whether symptoms should be interpreted as primary psychiatric illness, substance-related effects, medication withdrawal, or medical contributors. The single resolving rule is to anchor the case to timing of exposure and timing of symptom onset. If the symptom started after dose change, abrupt stop, intoxication, binge, or withdrawal window, do not rush to intensify chronic psychiatric medications.

Substance history should be concrete: drug, amount, route, frequency, last use, longest abstinence, prior withdrawal, seizures, delirium, overdose, treatment history, and relapse triggers. “Social drinking” is not enough. Likewise, benzodiazepine and alcohol history are high-yield because withdrawal may present as anxiety, tremor, tachycardia, insomnia, agitation, or perceptual disturbances. Stimulant use can mimic mania or panic. Heavy cannabis use can complicate anxiety, cognition, and psychosis interpretation. Nicotine changes the history because smoking status may alter CYP1A2-substrate antipsychotic exposure after admission or cessation.

Medical history matters because thyroid disease, seizure history, eating disorders, arrhythmia risk, pregnancy, liver disease, renal disease, and sleep apnea all alter medication safety. Psychiatric pharmacists are not expected to independently diagnose the medical condition, but they are expected to recognize when that history makes a drug choice unsafe or when urgent referral is required.

WHY THIS IS TESTED: stems often tempt learners to escalate antidepressants or antipsychotics when the better answer is first to recognize withdrawal, intoxication, or a medical contraindication hidden in the history.

Key rule: A vague symptom label such as “agitation” or “anxiety” is not enough. Always ask what changed first: medication, substance, or disease course.
Concept flow: Substance and medical history interpretation
Map the timeline
Place last substance use and recent medication changes on the symptom timeline.

Choose the driver
If exposure timing matches symptoms, suspect intoxication, withdrawal, or adverse effect first.

Check contraindications
Use medical history to screen for unsafe medication choices.

Escalate if needed
Severe withdrawal, overdose, or unstable medical risk requires urgent team notification.

B. Worked example

A 46-year-old man with major depressive disorder, alcohol use disorder, and hypertension presents to an outpatient behavioral health clinic for “worsening panic.” Medications are bupropion XL 300 mg orally every morning, trazodone 100 mg orally at bedtime, and lisinopril 20 mg orally daily. He reports tremor, insomnia, diaphoresis, and anxiety beginning 12 hours after his last drink; he drinks 10–12 beers nightly and had a withdrawal seizure 3 years ago. A distracting clue is that bupropion can worsen anxiety, making dose reduction seem attractive. The clinic pharmacist is asked for the most appropriate recommendation.

Reasoning chain: Identify task: determine whether this is panic worsening or substance-related danger. Extract key facts: heavy daily alcohol use, short interval since last use, autonomic symptoms, prior withdrawal seizure, bupropion on board. Apply rule: alcohol withdrawal history takes priority, and seizure risk is high; this is not a routine outpatient “panic medication adjustment” problem. Eliminate distractors: increasing trazodone or adding hydroxyzine addresses symptoms but misses the emergency risk; simply blaming bupropion is tempting but incomplete. Verify: recommend urgent evaluation/escalation for possible alcohol withdrawal and communicate that bupropion may further lower seizure threshold in this context.

C. Exam trap

Common wrong answer: Adjusting the chronic psychotropic first when acute substance withdrawal fits the timeline.
Why it is tempting: the patient is in a psychiatric clinic and symptoms overlap strongly with anxiety or mood disorders.
Single clue that eliminates it: the symptom cluster begins in a known withdrawal window after last use and is paired with prior severe withdrawal history.

D. Checkpoint

Question: A 29-year-old patient taking fluoxetine 20 mg orally daily reports new insomnia, anxiety, and palpitations. Which psychiatric history item most helps distinguish relapse from substance-related symptoms?

  1. Whether the patient has ever had counseling
  2. Whether the patient recently changed caffeine, stimulant, alcohol, or cannabis use
  3. Whether the patient prefers morning appointments
  4. Whether the patient had childhood bedwetting

Answer: B

  • A: Tempting because prior treatment engagement matters, but it does not rapidly distinguish symptom cause in this scenario.
  • B: Correct because recent substance changes can produce exactly this symptom cluster and alter interpretation of antidepressant response.
  • C: Tempting because scheduling can affect adherence, but it is not the discriminating history element here.
  • D: Tempting only as a broad developmental history clue, but it does not answer the immediate medication question.
If you missed this: Review 1.1.1.3 Substance use, withdrawal, and medical history — focus on the rule that timing of exposure versus symptom onset distinguishes relapse from intoxication or withdrawal.
High-Yield Connection: This concept overlaps heavily with Alcohol Withdrawal Recognition, Sedative And Stimulant Withdrawal, and Medication-Induced Psychiatric Symptoms. On exam day, know both the psychiatric presentation and the pharmacologic safety implication.
Pharmacist Action: NOTICE: autonomic symptoms, recent last use, or prior withdrawal complications. SAY: “Because these symptoms followed substance cessation and you have a seizure history, this needs urgent medical evaluation.” MONITOR: last use, withdrawal severity, seizure history, vitals if available, and interacting medications. HOLD/CLARIFY/ESCALATE: escalate immediately for suspected severe alcohol or sedative withdrawal, overdose risk, or unstable medical status.

1.1.1.4 Family, social, trauma, and adherence history: the hidden reasons regimens fail

A. Explanation

The decision conflict is whether poor outcomes reflect the wrong medication or the wrong fit for the patient’s context. The resolving rule is to identify whether access, insight, trauma triggers, caregiver support, stigma, or daily routine predict nonadherence or unsafe use. This is where many stems test advanced pharmacist thinking: not “What drug is first-line in theory?” but “What recommendation is most likely to succeed for this patient?”

Family history matters because bipolar disorder, suicide, substance use, and medication response in relatives may alter your level of caution or support a future recommendation. Social history matters because housing instability, food insecurity, transportation loss, shift work, childcare, legal stress, and language barriers can make once-daily oral therapy unrealistic. Trauma history can shape tolerability and acceptance; for example, sedation, weight changes, or sexual dysfunction may be especially unacceptable and drive silent nonadherence.

Adherence history should go beyond “Do you take your meds?” Ask how many doses were missed in the last week, how refills are obtained, whether side effects led to self-adjustment, whether the patient splits tablets, uses PRNs differently than prescribed, or stops medications when feeling better. Pharmacy claims, pill bottles, caregiver report, and previous discharge summaries often uncover discrepancies. This is where See Fig 6 becomes practical: the best medication decision may be impossible until the list is reconciled.

WHY THIS IS TESTED: board questions reward the candidate who notices that the apparently “best” drug is unrealistic because the patient cannot access it, cannot tolerate it, or will not reliably take it.

Concept flow: From social history to workable medication plan
Screen barriers
Ask about cost, transport, housing, routine, stigma, and caregiver support.

Choose fit
If the regimen does not fit real life, modify formulation, schedule, or support plan.

Verify adherence
Use fill history, collateral, and direct questioning rather than assumptions.

Target follow-up
Link the plan to feasible monitoring and team communication.

Memory anchor: Think FITS before calling a regimen failure: Finances, Insight, Transport/trauma, Support/schedule.

B. Worked example

A 27-year-old woman with bipolar disorder, obesity, and PTSD is seen after a psychiatric hospitalization discharge. Her prescribed regimen is lamotrigine 25 mg orally daily with weekly titration, quetiapine 300 mg orally nightly, and propranolol 10 mg orally twice daily as needed for anxiety. She says quetiapine “never works” and admits she takes it only on weekends because she works early shifts and cannot tolerate morning sedation. She also missed the lamotrigine for 6 consecutive days because the pharmacy was across town. A distracting clue is a family history of “antidepressants helping everyone,” which may lure the learner toward an SSRI-based answer. The team asks what most needs to be addressed in the history before declaring the current regimen ineffective.

Reasoning chain: Identify task: interpret apparent nonresponse. Extract key facts: major adherence barriers from sedation, work schedule, and pharmacy access; interrupted lamotrigine titration; PTSD symptoms as noise. Apply rule: a regimen cannot be judged ineffective if it is not being taken as intended; social and adherence history are central, not peripheral. Eliminate distractors: family response to antidepressants does not answer the current problem; simply increasing quetiapine ignores the reason it is not taken; adding another agent compounds complexity. Verify: recommend addressing sedation-related adherence, refill access, and safe lamotrigine retitration if interruption duration requires it per product labeling/local policy confirmation.

C. Exam trap

Common wrong answer: Escalating dose when the true issue is nonadherence driven by side effects or access barriers.
Why it is tempting: symptoms remain uncontrolled, so increasing intensity feels proactive.
Single clue that eliminates it: the patient explicitly reports not taking the medication as prescribed due to a practical barrier or intolerable adverse effect.

D. Checkpoint

Question: A patient prescribed aripiprazole 10 mg orally daily after discharge says he has “failed” it because hallucinations returned. Which psychiatric history detail most changes the pharmacist recommendation?

  1. Whether he likes taking tablets with juice
  2. Whether the family history includes panic disorder
  3. Whether he filled the medication and has taken it consistently since discharge
  4. Whether he had chickenpox as a child

Answer: C

  • A: Tempting because administration preferences can matter, but it does not resolve the claim of treatment failure.
  • B: Tempting because family history is relevant in some cases, but it is not the key determinant of current efficacy interpretation.
  • C: Correct because adherence and fill completion decide whether recurrence reflects drug failure or no effective exposure.
  • D: Plausible as a background medical history item, but unrelated to the present medication question.
If you missed this: Review 1.1.1.4 Family, social, trauma, and adherence history — focus on the rule that uncontrolled symptoms cannot prove inefficacy if the regimen was not actually implemented.
Quick Recall:

  • True or False: A medication can be labeled ineffective even if the patient never filled it.
  • The best single collateral source for recent medication possession is the ______ history.
  • Name 3 social barriers that commonly masquerade as “medication failure.”
Pharmacist Action: NOTICE: early refill gaps, sedation complaints, transportation issues, and complex schedules. SAY: “Your symptoms may reflect that the regimen does not fit your routine; let’s identify what is getting in the way before changing classes.” MONITOR: refill interval, missed doses, side-effect burden, and follow-up attendance. HOLD/CLARIFY/ESCALATE: clarify before dose escalation if uncontrolled symptoms occur with clear access or adherence barriers.

1.1.1.5 Safety history and pharmacist synthesis: what requires immediate clarification or escalation?

A. Explanation

The final decision conflict is whether the history supports routine optimization or whether it contains a red flag that changes the priority to immediate clarification, withholding a recommendation, or urgent escalation. The resolving rule is to screen every history for safety-critical items before discussing fine points of efficacy.

High-priority psychiatric history items include current or recent suicidality, self-harm behavior, homicidal threats, overdose, access to lethal means, severe agitation with intoxication, recent abrupt withdrawal from alcohol or sedative-hypnotics, serotonin syndrome features after serotonergic exposure, NMS-like history after antipsychotics, clozapine-related neutropenia, severe rash with lamotrigine or carbamazepine, pregnancy considerations, and major interaction risks from current medication or substance use. In board-style practice, the pharmacist does not independently determine legal disposition, but must promptly notify the team, recommend urgent evaluation, or activate protocol when safety demands it.

History synthesis means prioritizing the one finding that changes management first. If a patient has insomnia, low mood, and missed doses, but also has escalating suicidal thoughts and stockpiled medications, the history is not “depression follow-up”; it is a safety escalation case. If a patient requests antidepressant restart but reports prior SSRI-induced mania, that single clue outranks routine depression treatment logic. If a patient has psychotic relapse and stopped smoking on admission, antipsychotic concentration changes may matter, but safety still starts with risk assessment and medication reconciliation. See Fig 5 for the sequence.

WHY THIS IS TESTED: the exam often measures whether you can shift from optimization thinking to urgent safety thinking based on one history red flag.

Concept flow: Safety-first synthesis of psychiatric history
Review the history
Collect symptom, medication, substance, medical, social, and collateral details.

Screen for red flags
Suicidality, severe withdrawal, overdose, serious reaction history, or dangerous interactions change priority.

Decide action level
Routine optimization, urgent clarification, or immediate escalation.

Document and communicate
State the key history clue, the medication implication, and the monitoring plan.

B. Worked example

A 38-year-old man with depression, chronic pain, and insomnia presents for refill review. Current medications are duloxetine 60 mg orally daily, trazodone 150 mg orally nightly, gabapentin 600 mg orally three times daily, and tramadol 50 mg orally every 6 hours as needed from another prescriber. He reports worsening mood and requests a higher duloxetine dose. A distracting clue is neuropathic pain, which could support escalation. However, he also reveals that he stopped all medications for 5 days last month “to save them,” resumed them all at once, has had passive death wishes, and recently stockpiled unused tablets after a breakup.

Reasoning chain: Identify task: determine whether this is routine antidepressant adjustment. Extract key facts: suicidality-related warning, medication stockpiling, variable adherence, serotonergic/polypharmacy exposure. Apply rule: safety red flags override routine dose optimization; pharmacist role is to urgently notify the team and clarify overdose risk, not simply recommend a dose increase. Eliminate distractors: increasing duloxetine for pain is superficially attractive; focusing only on adherence counseling misses acute risk; dismissing the stockpile because thoughts are “passive” is unsafe. Verify: escalate promptly, communicate overdose and serotonergic risk, and recommend immediate prescriber/team review.

C. Exam trap

Common wrong answer: Proceeding directly to optimization because the patient’s chief complaint sounds routine.
Why it is tempting: the stem begins like a standard antidepressant follow-up and includes a medication-based rationale for adjustment.
Single clue that eliminates it: any active safety signal such as suicidality with stockpiled medication, recent overdose, or severe withdrawal history changes the task from optimization to escalation.

D. Checkpoint

Question: Which psychiatric history finding most requires immediate clarification before recommending a routine antidepressant increase?

  1. Family history of seasonal depression
  2. Past benefit from cognitive behavioral therapy
  3. Recent medication stockpiling with escalating suicidal thoughts
  4. Preference for bedtime dosing

Answer: C

  • A: Tempting because family history can shape formulation of the case, but it is not the urgent deciding clue.
  • B: Tempting because prior benefit informs comprehensive care, but it does not outrank an immediate safety issue.
  • C: Correct because stockpiling plus suicidal thoughts creates acute overdose concern and requires urgent team communication before routine adjustment.
  • D: Tempting because dosing preference may improve adherence, but it is irrelevant compared with imminent safety risk.
If you missed this: Review 1.1.1.5 Safety history and pharmacist synthesis — focus on the rule that safety red flags override routine efficacy optimization.
Pharmacist Action: NOTICE: suicidality, stockpiling, overdose, severe withdrawal, serious prior reactions, or high-risk interaction patterns. SAY: “This history raises an immediate safety concern that needs prompt team evaluation before we make a routine medication change.” MONITOR: access to medications, timing of risk statements, recent adherence disruptions, and co-prescribed high-risk agents. HOLD/CLARIFY/ESCALATE: escalate immediately for active or escalating self-harm risk, overdose concern, severe withdrawal, or suspected serious drug reaction.

Exam Traps & Differentiators

Most common wrong answer and why: Calling a regimen “ineffective” without proving adequate exposure. This is tempting because stems often list persistent symptoms and multiple prior medications. The differentiator is whether the patient actually took a therapeutic dose for long enough, without confounding discontinuation or substance-related symptoms.

Looks similar Actually is Single discriminator Medication implication
Relapse of anxiety/depression SSRI discontinuation Symptoms begin soon after abrupt stop or missed doses Do not declare current replacement ineffective too early
Antidepressant nonresponse Inadequate trial Low dose, short duration, or poor adherence Clarify before augmenting or switching
Panic worsening Alcohol or sedative withdrawal Last use timing plus autonomic symptoms or seizure history Urgent evaluation may be needed
Psychosis despite treatment No medication access after discharge Refill gap or never-filled prescription Address transitions-of-care barrier before changing class
Routine depression follow-up Acute safety escalation Suicidal thoughts with stockpiled medication or recent overdose Urgent team notification before routine optimization
If the stem says... Think...
“Several antidepressants failed” Were they adequate trials, and were they actually taken?
“Anxiety worsened after medication change” Withdrawal or activation timeline before assuming disease progression
“Psychosis recurred after discharge” Medication reconciliation, fill history, and adherence barriers
“Patient wants a higher dose today” Safety screen first: suicidality, overdose, substance withdrawal, serious reactions
“No side effects reported” Patients may have self-discontinued; ask directly about sedation, weight, sexual dysfunction, EPS, and stigma
“Family member says they did better before” Collateral may reveal the most effective prior regimen and the real reason it was stopped

Related future trap: in Mental Status Exam Findings, learners often confuse a historical report of hallucinations with current active perceptual disturbance. History tells you what has happened over time; MSE tells you what is present now. Related future trap in Screening And Monitoring Scales: symptom severity scores do not replace a good medication and safety history.

Review connection: The traps above test history interpretation as a medication-decision tool. If any felt unfamiliar, revisit 1.1.1.2 Past psychiatric and medication history and 1.1.1.5 Safety history and pharmacist synthesis before attempting the Self-check quiz.

Tables

History element What to ask Why it matters for medication decisions
Current symptom timeline When did symptoms start and what changed first? Distinguishes relapse from withdrawal, activation, or intoxication
Past medication trials Drug, dose, duration, adherence, benefit, adverse effects Determines true nonresponse versus inadequate trial
Prior serious reactions Rash, NMS, serotonin syndrome, severe EPS, neutropenia May eliminate re-exposure or require urgent clarification
Substance use Type, amount, route, last use, withdrawal history Explains symptoms and modifies safety planning
Medical comorbidities Seizures, arrhythmia risk, renal/hepatic disease, pregnancy Changes drug selection, interactions, and monitoring
Adherence/access Missed doses, refill gaps, cost, transportation, side-effect burden Prevents false labeling of medication failure
Family history Bipolar disorder, suicide, substance use, strong medication response Supports risk assessment and treatment interpretation
Safety history Suicidality, self-harm, overdose, stockpiling, lethal means May require immediate team notification or emergency referral
Comparison point True medication failure Intolerance Inadequate trial/nonadherence
Dose Therapeutic May be therapeutic or low Often subtherapeutic or inconsistent
Duration Adequate May stop early due to side effects Often too short to judge
Adherence Consistent Usually consistent until adverse effect Interrupted, missed, or never filled
Outcome statement No meaningful benefit despite adequate exposure Benefit limited by unacceptable harm Outcome uninterpretable
Exam action Consider switch or augmentation Consider mitigation or alternative Clarify before changing strategy
Differential history pattern Key clue Likely interpretation Pharmacist-facing next step
Anxiety after stopping paroxetine Abrupt cessation and rapid onset Antidepressant discontinuation Clarify stop history before labeling the new drug ineffective
Agitation after antipsychotic increase Recent dose increase, inner restlessness Akathisia possibility Assess adverse effect rather than assuming worsening psychosis
Tremor, diaphoresis, insomnia after last drink Withdrawal window and prior seizure Alcohol withdrawal Urgent escalation and medication-risk review
Relapse after discharge Prescription never picked up No effective maintenance exposure Address access and reconciliation first
Request for routine refill change Medication stockpiling plus suicidal ideation Acute safety concern Notify team immediately before routine optimization

Algorithm / Approach

Concept flow: Pharmacist approach to psychiatric history in exam stems
Identify the task
Is the stem asking about drug choice, dose change, monitoring, adherence, or safety escalation?

Extract the deciding history clue
Look first for prior response, serious reaction, missed doses, abrupt stop, last substance use, or suicidality.

Classify the problem
True nonresponse, intolerance, withdrawal/intoxication, nonadherence, access barrier, or safety emergency.

Choose the recommendation
Optimize, clarify before changing, document and monitor, or urgently escalate to the team.

Verify scope
Stay within pharmacist role: recommend, reconcile, monitor, counsel, and escalate when red flags appear.

History-to-action decision tree
Exam takeaway: Convert each history clue into one of four actions—optimize, clarify, monitor, or escalate.
flowchart TD
A[History clue identified] --> B{Safety red flag?}
B -- Yes --> C[Escalate urgently]
B -- No --> D{Adequate prior trial?}
D -- No --> E[Clarify before switching]
D -- Yes --> F{Helpful but intolerable?}
F -- Yes --> G[Mitigate or choose alternative]
F -- No --> H{Adherence/access barrier?}
H -- Yes --> I[Fix implementation plan]
H -- No --> J[Optimize regimen]

Rapid Review

  • Prior trial quality → dose + duration + adherence separate true failure from noise
  • Symptoms after abrupt SSRI stop → think discontinuation before relapse
  • “Panic” after last drink → withdrawal timing outranks routine anxiolytic adjustment
  • Past benefit on one antipsychotic → stopped-for-cost differs from stopped-for-nonresponse
  • Family bipolar history → increases caution with unopposed antidepressant interpretation
  • Medication list disagreement → patient report plus fill history beats chart list alone
  • Return of symptoms after discharge → first ask whether the prescription was filled
  • Severe prior reaction → avoid casual rechallenge until exact event clarified
  • Stockpiling medication → safety escalation, not routine dose titration
  • Side-effect-driven missed doses → implementation failure, not necessarily class failure
  • Substance use history → quantity, last use, and withdrawal history beat vague labels
  • Social barriers → regimen fit can matter more than theoretical first-line status
  • Collateral from family/caregiver → often reveals actual adherence and prior stability pattern
Memory anchor: For board stems, ask “What changed first?” If symptoms follow a stop, start, dose change, or substance shift, the answer is often not “the disease got worse.”

Self-check quiz

1. A 33-year-old man with major depressive disorder and GERD is taking escitalopram 10 mg orally daily for 12 days and omeprazole 20 mg orally daily. The prescriber asks whether to add augmentation because the patient reports no improvement yet. Which history detail is most appropriate to clarify first?

  1. Whether the escitalopram trial has reached an adequate duration with consistent adherence
  2. Whether the patient prefers capsules over tablets
  3. Whether the patient’s cousin responded to sertraline
  4. Whether the patient drinks tea in the evening

2. A 40-year-old woman with panic symptoms and chronic insomnia takes paroxetine 40 mg orally daily but stopped it abruptly 4 days ago after running out. She now reports dizziness, anxiety, and “electric shock” sensations. Which history interpretation is most appropriate?

  1. Probable immediate antidepressant class failure
  2. Probable discontinuation symptoms after abrupt SSRI cessation
  3. Proof that she requires an antipsychotic
  4. Evidence that paroxetine caused treatment-resistant panic disorder

3. A 51-year-old man with schizophrenia, obesity, and type 2 diabetes is prescribed olanzapine 15 mg orally nightly after an inpatient stay. At follow-up, he reports worsening hallucinations. Fill records show the prescription was never picked up because of cost, and he has been taking leftover risperidone 1 mg orally at bedtime every few days. What is the most appropriate pharmacist interpretation?

  1. Olanzapine failed despite an adequate trial and should be avoided
  2. The recurrence most likely reflects nonadherence and access barriers rather than true olanzapine failure
  3. Risperidone 1 mg every few days proves antipsychotic class resistance
  4. The main issue is that bedtime dosing is always ineffective for psychosis

4. A 45-year-old woman with depression, alcohol use disorder, and hypertension takes bupropion XL 300 mg orally every morning and trazodone 100 mg orally nightly. She presents to clinic with tremor, diaphoresis, insomnia, and anxiety 10 hours after her last alcohol intake. She had a prior alcohol-withdrawal seizure. Which recommendation is most appropriate?

  1. Increase bupropion XL to 450 mg orally every morning for worsening mood
  2. Recommend urgent medical evaluation for possible alcohol withdrawal and communicate seizure risk
  3. Continue current medications and reassess in 4 weeks because symptoms may be anxiety relapse
  4. Increase trazodone to 200 mg orally nightly as the best initial step

5. A 28-year-old woman with bipolar disorder and PTSD takes quetiapine 300 mg orally nightly and lamotrigine 50 mg orally daily. She reports persistent symptoms and says quetiapine “does nothing,” but then states she takes it only on weekends due to sedation before early work shifts. Which is the most appropriate pharmacist conclusion?

  1. Quetiapine is ineffective and should be replaced immediately
  2. The symptom persistence cannot be interpreted as drug failure until adherence and regimen fit are addressed
  3. PTSD always explains nonresponse to bipolar medications
  4. Lamotrigine should be doubled first because it has fewer sedative effects

6. A 37-year-old man with major depressive disorder, neuropathic pain, and insomnia takes duloxetine 60 mg orally daily, trazodone 150 mg orally nightly, gabapentin 600 mg orally three times daily, and tramadol 50 mg orally every 6 hours as needed. He requests a duloxetine increase because his mood is worse. During review, he reports passive death wishes and says he has stockpiled extra tablets after missed refill pickups. Which is the most appropriate next step for the pharmacist?

  1. Recommend increasing duloxetine to 90 mg orally daily because pain and mood both remain uncontrolled
  2. Recommend urgent team notification and safety evaluation before routine antidepressant adjustment
  3. Recommend stopping trazodone only because it may contribute to oversedation
  4. Recommend outpatient follow-up in 1 month because passive thoughts alone are low risk

7. A 32-year-old woman with depression and obesity is taking sertraline 50 mg orally daily for 3 weeks after abruptly stopping paroxetine 40 mg orally daily when she ran out. She reports anxiety, nausea, insomnia, and feeling “wired.” She also drinks three energy drinks daily and takes ondansetron 4 mg orally as needed for migraine-associated nausea. Which interpretation is most appropriate?

  1. This proves sertraline nonresponse, so immediate augmentation is required
  2. The symptoms are most consistent with a history that requires clarification for discontinuation and activation before labeling treatment failure
  3. The only important clue is ondansetron use, so the syndrome should be treated as serotonin syndrome
  4. The energy drinks fully explain the case, so the antidepressant timeline can be ignored

8. A 60-year-old man with schizoaffective disorder, CKD stage 3, and tobacco use disorder was stable for years on clozapine per family report but presents after 2 months off medications when his pharmacy closed. Current chart allergies list “antipsychotics—bad reaction,” but no details are available. He now takes no psychotropics, smokes one pack per day, and has recurrent psychosis. Which history element most requires clarification before any specific antipsychotic recommendation is finalized?

  1. The exact nature of the prior “bad reaction,” including whether it represented a serious reaction versus nonspecific intolerance
  2. Whether he prefers blister packs to bottles
  3. Whether his cousin had depression
  4. Whether he drinks coffee after dinner

Answer key

1. Question 1

Correct answer: A

  • A: Tempting because it may feel too basic, but it is correct: escitalopram 10 mg daily for 12 days is usually too early to label ineffective, and adherence must be confirmed before augmentation. The discriminating clue is the short treatment duration. Authoritative support: Lexicomp SSRI monographs; DiPiro Pharmacotherapy principles of antidepressant trial assessment.
  • B: Tempting because formulation preference can influence adherence, but the single fact that eliminates it is that no adequate trial has yet occurred. Source support: antidepressant evaluation principles in AHFS and standard psychopharmacology texts.
  • C: Tempting because family response can inform future selection, but it does not answer whether this patient’s current trial is interpretable. The discriminating clue is the patient’s own early course on therapy. Source: DiPiro; Clinical Pharmacology drug class guidance.
  • D: Tempting because caffeine or tea can worsen insomnia or anxiety, but evening tea does not supersede the need to verify adequate duration and adherence. The discriminating clue is the 12-day escitalopram exposure. Source: Lexicomp and antidepressant monitoring guidance.
If you missed this: Review 1.1.1.1 Foundational structure — focus on the adequacy-of-trial rule before labeling antidepressant failure.

2. Question 2

Correct answer: B

  • A: Tempting because symptoms returned after the medication was stopped, but abrupt cessation with dizziness and “electric shocks” points to discontinuation rather than class failure. The discriminating clue is the abrupt stop 4 days ago. Source: Lexicomp paroxetine monograph; FDA labeling and psychopharmacology references on SSRI discontinuation.
  • B: Correct because paroxetine has a high discontinuation-risk profile, and the symptom cluster plus timing strongly supports discontinuation syndrome. The discriminating clue is the rapid onset after running out. Source: Lexicomp; AHFS Drug Information.
  • C: Tempting because severe distress can push learners toward “stronger” therapy, but no psychosis clue is provided. The discriminating clue is the classic sensory symptom description. Source: standard antidepressant discontinuation references.
  • D: Tempting because panic symptoms are present, but the single fact that eliminates it is that symptoms track abrupt drug cessation, not adequate exposure failure. Source: DiPiro and antidepressant practice references.
If you missed this: Review 1.1.1.3 Substance use, withdrawal, and medical history — focus on the timeline rule: what changed first?

3. Question 3

Correct answer: B

  • A: Tempting because hallucinations persist and olanzapine carries metabolic burden, but the drug was never picked up, so no adequate trial occurred. The discriminating clue is the fill record showing zero possession. Source: Lexicomp olanzapine monograph; ASHP medication reconciliation principles.
  • B: Correct because the recurrence is best explained by access-related nonadherence and inconsistent subtherapeutic leftover use. The discriminating clue is the never-filled discharge prescription. Source: ASHP transitions-of-care guidance; DiPiro adherence principles.
  • C: Tempting because another antipsychotic was used and symptoms persisted, but risperidone 1 mg every few days is not an interpretable antipsychotic trial. The discriminating clue is the clearly inadequate dose pattern. Source: Lexicomp risperidone monograph.
  • D: Tempting only if a learner overfocuses on administration timing; bedtime dosing is common and does not explain the failure here. The discriminating clue remains the prescription nonfill. Source: standard antipsychotic dosing references.
If you missed this: Review 1.1.1.4 Family, social, trauma, and adherence history — focus on fill history as the discriminator between nonresponse and no exposure.

4. Question 4

Correct answer: B

  • A: Tempting because depression is present and bupropion is already in use, but the single fact that eliminates it is suspected alcohol withdrawal with prior seizure history; also, bupropion may worsen seizure risk. Source: FDA bupropion labeling; Lexicomp.
  • B: Correct because tremor, diaphoresis, insomnia, and anxiety soon after last drink with prior withdrawal seizure indicate urgent risk. The discriminating clue is the prior alcohol-withdrawal seizure. Source: ASAM alcohol withdrawal guidance; Lexicomp bupropion safety information.
  • C: Tempting because anxiety relapse is plausible, but the timing after last alcohol use and seizure history make watchful waiting unsafe. Source: ASAM guidance and withdrawal references.
  • D: Tempting because trazodone may help insomnia, but it does not address the acute withdrawal syndrome or seizure risk. The discriminating clue is the withdrawal window with autonomic symptoms. Source: alcohol withdrawal guidelines.
If you missed this: Review 1.1.1.3 Substance use, withdrawal, and medical history — focus on the exposure-to-symptom timeline and severe withdrawal red flags.

5. Question 5

Correct answer: B

  • A: Tempting because symptoms persist and quetiapine can be sedating, but the drug’s efficacy cannot be judged when it is taken only on weekends. The discriminating clue is inconsistent administration due to sedation and schedule mismatch. Source: Lexicomp quetiapine monograph; adherence principles in psychopharmacology texts.
  • B: Correct because the regimen has not been implemented as prescribed, so the right move is to address adherence and fit before declaring failure. The discriminating clue is weekend-only use. Source: DiPiro; ASHP transitions-of-care and adherence guidance.
  • C: Tempting because comorbidity can complicate symptom interpretation, but PTSD does not explain away the adherence problem. The discriminating clue is the self-reported nonadherence reason. Source: psychopharmacology treatment-interpretation principles.
  • D: Tempting because lamotrigine is less sedating, but doubling it first ignores the primary reason symptoms remain uncontrolled and could create unsafe titration issues depending on interruption history. Source: FDA lamotrigine labeling; Lexicomp.
If you missed this: Review 1.1.1.4 Family, social, trauma, and adherence history — focus on regimen fit as the discriminator before dose escalation.

6. Question 6

Correct answer: B

  • A: Tempting because duloxetine could reasonably be increased for pain and mood in some patients, but the single fact that eliminates it is passive death wishes plus stockpiled medication, which raises overdose concern. Source: FDA duloxetine labeling; suicide-risk management principles in psychiatric pharmacy references.
  • B: Correct because safety red flags override routine antidepressant optimization; pharmacist action is urgent notification and evaluation. The discriminating clue is stockpiling combined with suicidal ideation. Source: APA-related suicide risk principles; ASHP patient safety guidance; Lexicomp interaction/safety monographs.
  • C: Tempting because trazodone contributes to polypharmacy and sedation, but focusing narrowly on one drug misses the immediate self-harm risk. The discriminating clue is the safety history, not just polypharmacy. Source: Lexicomp and clinical safety guidance.
  • D: Tempting because “passive” may sound less urgent, but medication stockpiling makes delayed follow-up unsafe. The discriminating clue is preparation/access to means. Source: suicide-risk assessment standards and psychiatric pharmacy safety practice.
If you missed this: Review 1.1.1.5 Safety history and pharmacist synthesis — focus on the rule that stockpiling plus suicidality changes the action from optimize to escalate.

7. Question 7

Correct answer: B

  • A: Tempting because symptoms continue despite 3 weeks of sertraline, but the single fact that eliminates it is abrupt paroxetine discontinuation just before the switch, making discontinuation and early activation plausible. Source: Lexicomp sertraline and paroxetine monographs.
  • B: Correct because the history contains multiple confounders—abrupt SSRI stop, early new-trial timing, and stimulant intake—so treatment failure cannot yet be declared. The discriminating clue is the medication transition timeline. Source: AHFS and standard antidepressant switching guidance.
  • C: Tempting because ondansetron and serotonergic agents may trigger concern, but classic serotonin syndrome features are not provided, and the history fits a more common alternative. The discriminating clue is the abrupt paroxetine cessation with discontinuation-type symptoms. Source: FDA labeling and serotonin syndrome references.
  • D: Tempting because three energy drinks daily can worsen anxiety and insomnia, but saying they “fully explain” the case ignores the more important SSRI transition history. The discriminating clue is the temporal relationship to stopping paroxetine. Source: psychopharmacology transition principles.
If you missed this: Review 1.1.1.2 Past psychiatric and medication history and 1.1.1.3 Substance use, withdrawal, and medical history — focus on how abrupt discontinuation can mimic relapse during a new antidepressant trial.

8. Question 8

Correct answer: A

  • A: Correct because “bad reaction” is too vague to support safe antipsychotic selection; the difference between severe EPS, NMS, neutropenia, sedation, or “felt bad” radically changes the recommendation. The discriminating clue is the undocumented allergy label paired with a strong family report of prior stability on clozapine. Source: FDA clozapine labeling; Lexicomp antipsychotic safety monographs.
  • B: Tempting because packaging may improve adherence, especially in a patient with pharmacy disruption, but it does not resolve whether a class-limiting serious reaction occurred. Source: adherence literature and ASHP transitions guidance.
  • C: Tempting only as broad family context, but it does not affect immediate antipsychotic safety selection. The discriminating clue is the antipsychotic reaction history. Source: psychopharmacology safety principles.
  • D: Tempting because caffeine can affect sleep and anxiety, but it does not outrank the need to clarify a potentially dangerous prior reaction. The discriminating clue is the vague allergy documentation. Source: Lexicomp and product labeling.
If you missed this: Review 1.1.1.2 Past psychiatric and medication history — focus on clarifying prior serious reactions versus nonspecific intolerance before re-exposure to antipsychotics.

References

  • Lexicomp Online. Wolters Kluwer Clinical Drug Information. Psychotropic drug monographs. Accessed 2026.
  • American Society of Health-System Pharmacists. AHFS Drug Information. Bethesda, MD: ASHP; latest edition.
  • DiPiro, Joseph T., et al., editors. Pharmacotherapy: A Pathophysiologic Approach. Latest edition. McGraw-Hill.
  • American Society of Addiction Medicine. The ASAM Clinical Practice Guideline on Alcohol Withdrawal Management.
  • U.S. Food and Drug Administration. Approved prescribing information for paroxetine, sertraline, bupropion, lamotrigine, clozapine, and antipsychotic/antidepressant agents referenced in this lesson.

Last reviewed: March 15, 2026

Lesson 2

Mental Status Exam Findings

Illustrations

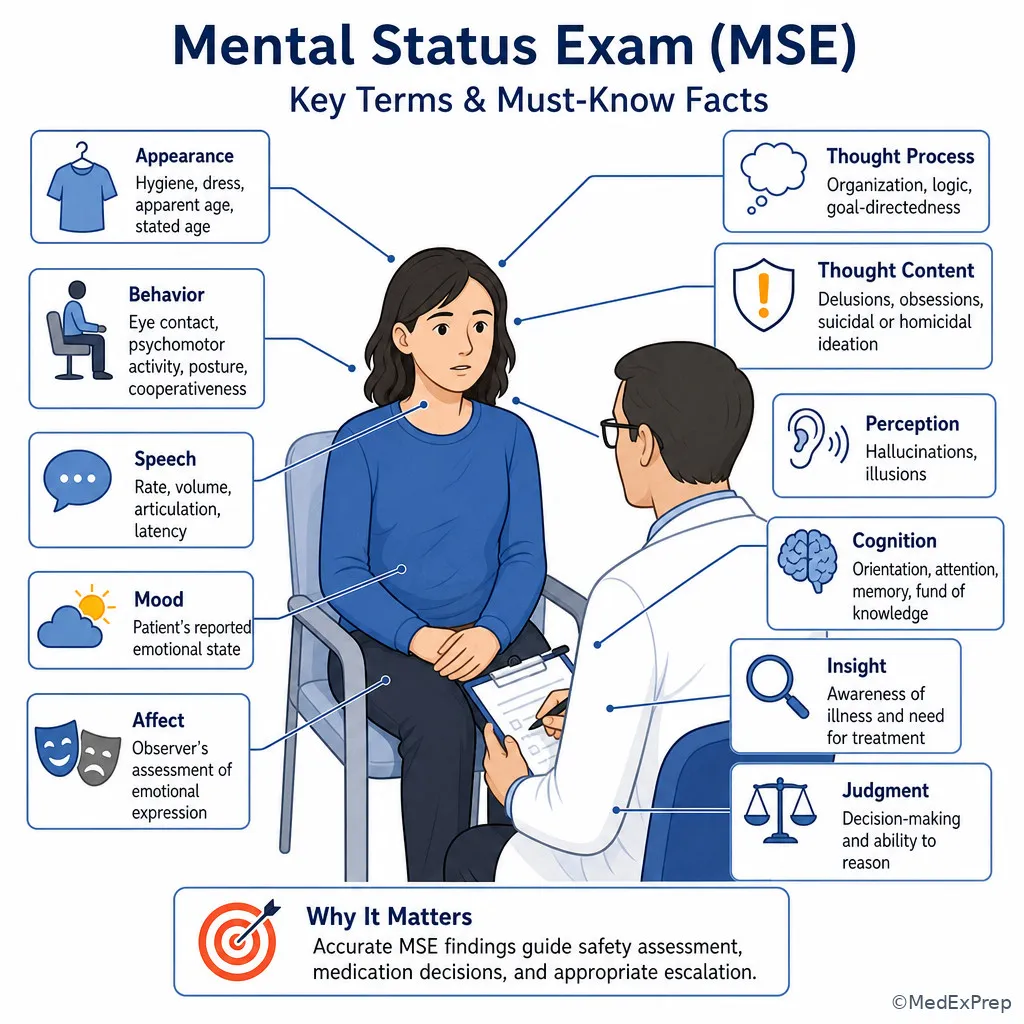
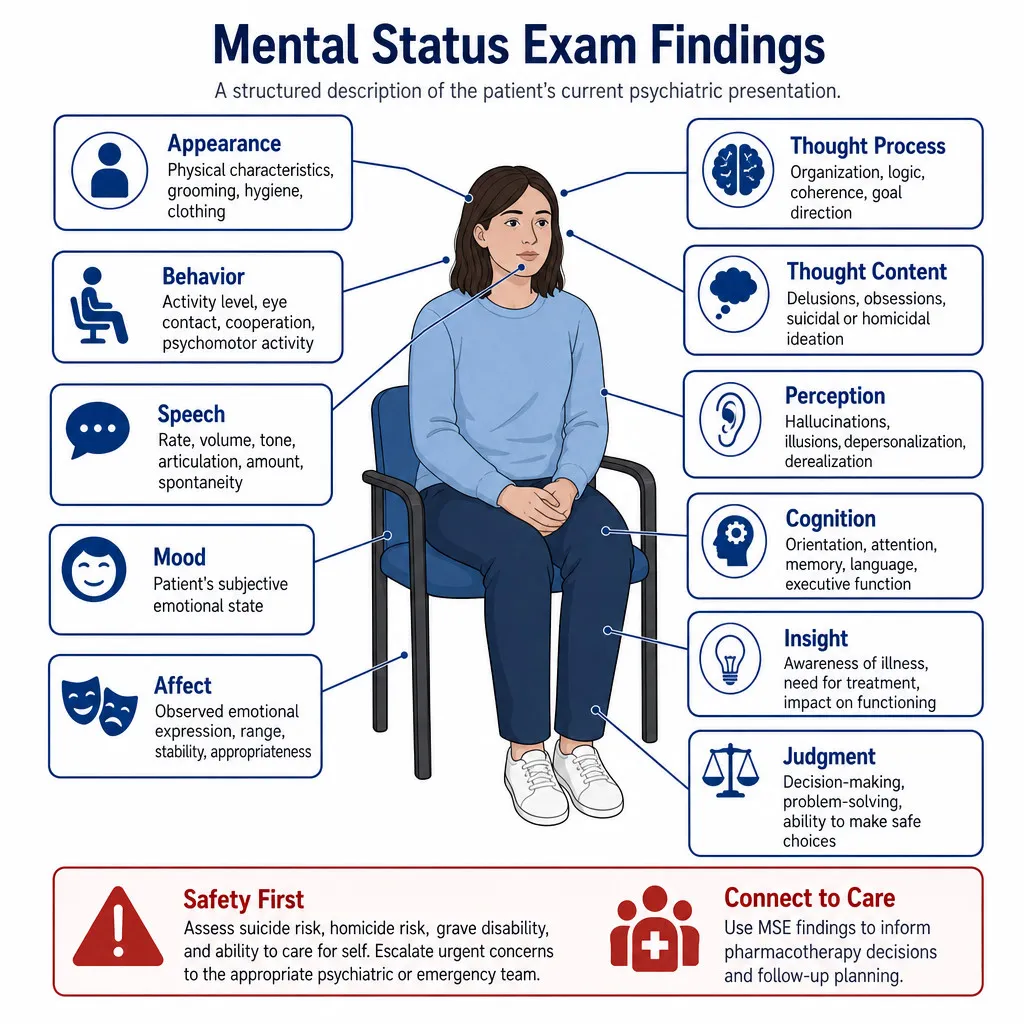
Illustration: Mental Status Exam Findings
Exam takeaway: Use this visual to recall the key testable points for Mental Status Exam Findings.
Illustration: Mental Status Exam Findings
Illustration: Why it matters
Exam takeaway: Use this visual to recall the key testable points for Why it matters.
Illustration: Why it matters
Illustration: Key Terms & Must-Know Facts
Exam takeaway: Use this visual to recall the key testable points for Key Terms & Must-Know Facts.
Illustration: Key Terms & Must-Know Facts
Illustration: Core content
Exam takeaway: Use this visual to recall the key testable points for Core content.
Illustration: Core content

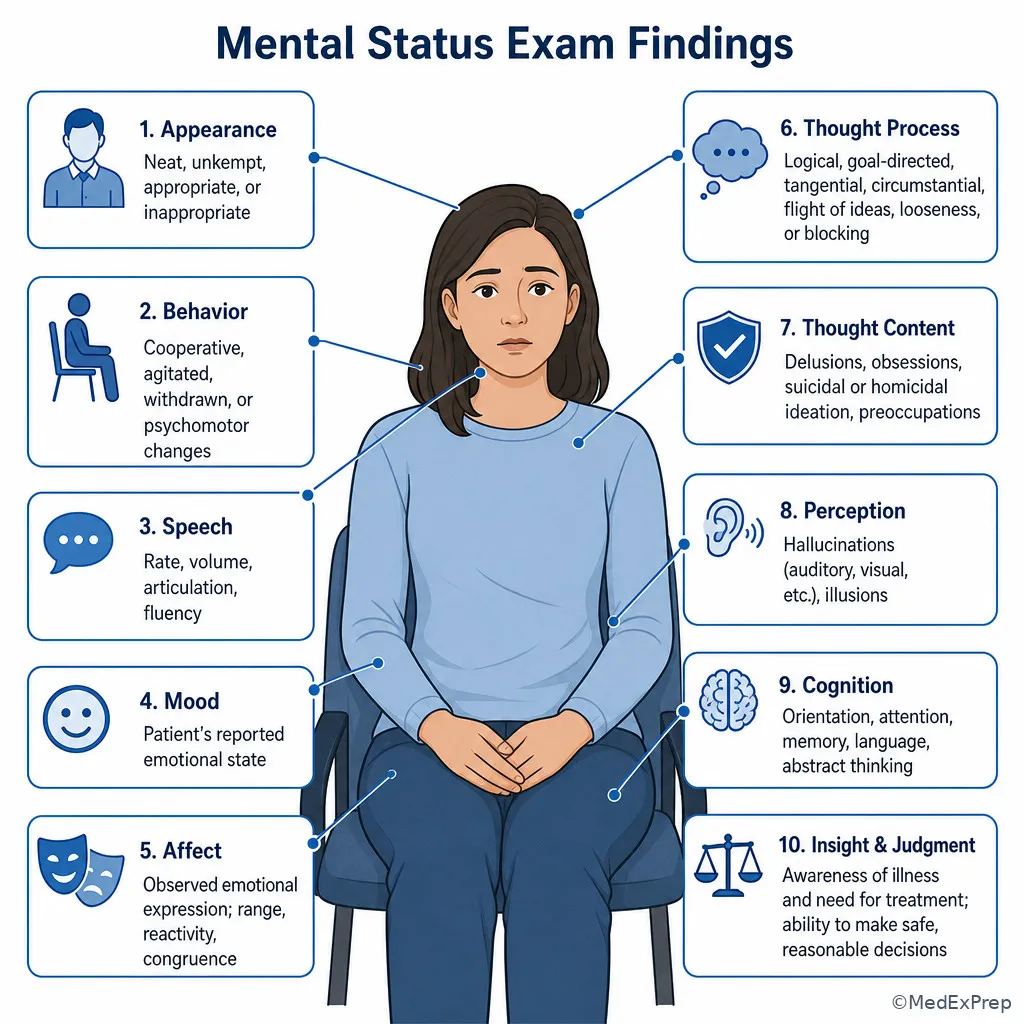
Mental Status Exam Findings

The mental status examination (MSE) is a structured description of the patient's current psychiatric presentation. For the BCPP candidate, the highest-yield task is not to perform an unrestricted diagnostic interview, but to recognize medication-relevant findings, distinguish commonly confused MSE domains, connect observations to safety and pharmacotherapy decisions, and escalate urgent concerns to the appropriate psychiatric or emergency team.

What you'll learn

  • Blueprint 1.6 - Psychiatric interview: Distinguish appearance, behavior, speech, mood, affect, thought process, thought content, perception, cognition, insight, and judgment in a pharmacist-facing assessment.
  • Blueprint 1.8 - Health and medication history: Integrate current MSE findings with medication exposure, adherence, previous response, and collateral information rather than interpreting a finding in isolation.
  • Blueprint 1.14 - Adverse effects and drug-related problems: Recognize MSE findings that may indicate excessive sedation, activation, movement-related effects, withdrawal, intoxication, or another medication-related safety problem.
  • Blueprint 1.15 - Medications, substances, and diseases that can cause or worsen psychiatric symptoms: Identify when a change in mental status should trigger review of medications, substances, medical contributors, and recent regimen changes.
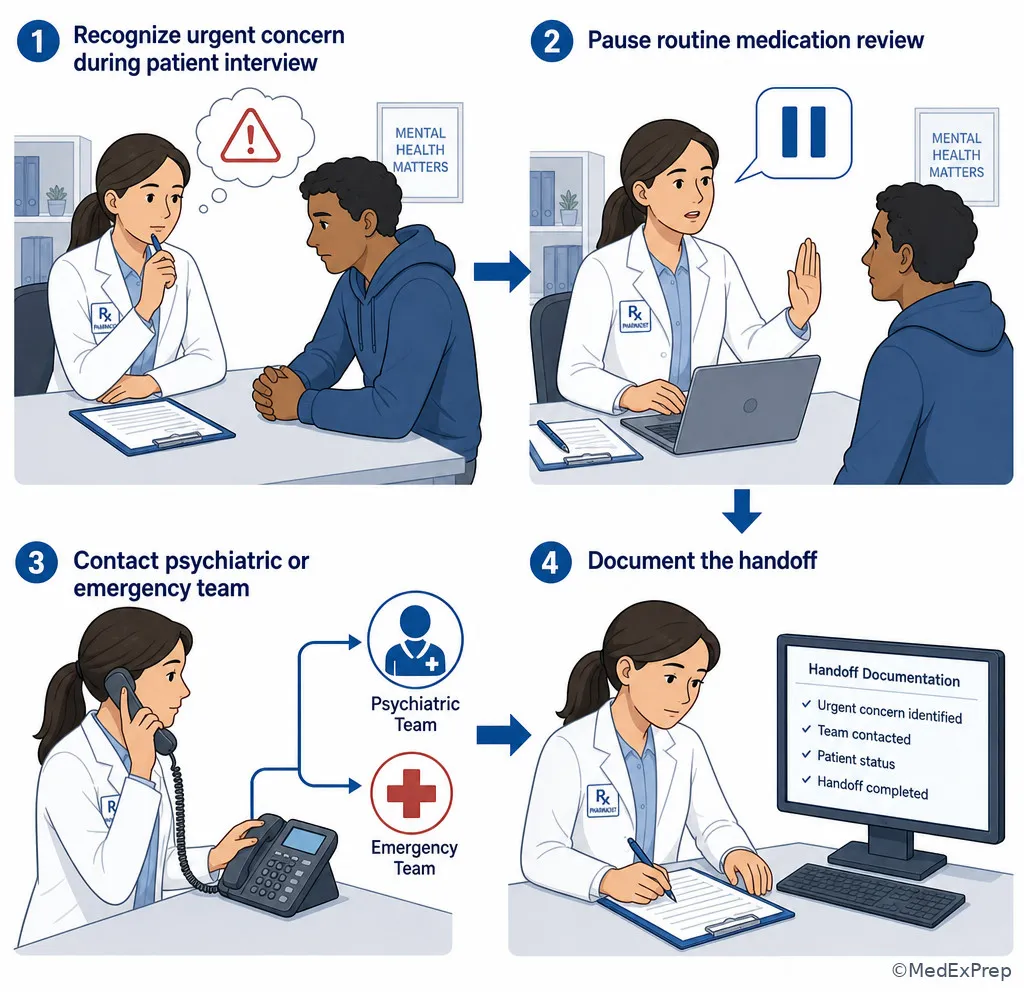
  • Patient-safety subskill: Escalate suicidality, homicidality, severe disorganization, marked alteration in cognition, dangerous behavior, or other urgent concerns rather than acting outside pharmacist authority.

Blueprint mapping

Person-Centered Care - 65% of the supplied BCPP blueprint excerpt -> psychiatric interview and MSE; health and medication history; physical and laboratory assessment as relevant; adverse effects and medication-related psychiatric symptoms; comprehensive medication management; documentation and interprofessional coordination.

Estimated time: 35-50 minutes

Prereqs: Psychiatric History Components

Key outputs: You should be able to choose the correct MSE domain for a finding, separate observation from patient report, identify medication-safety implications, and choose escalation or medication-focused follow-up when the presentation requires action outside pharmacist authority.

Why it matters

  • Board-style cases often embed a short behavioral observation or patient statement and ask what it means for medication safety, monitoring, or the next pharmacist action.
  • The MSE is a current-state snapshot. A single finding should be interpreted with the medication history, recent changes, substance exposure, medical context, and longitudinal course.
  • Several domains are deliberately easy to confuse: mood versus affect, thought process versus thought content, and perception versus belief content.
  • Urgent safety findings change the priority of the encounter: the pharmacist should communicate and escalate rather than continue routine medication optimization while an immediate risk is unresolved.
Fig 1. Mental status exam domain map
Exam takeaway: First classify the finding into the correct MSE domain, then decide whether it changes medication safety, monitoring, or escalation.
graph TD
A[MSE finding] --> B[Observable presentation]
A --> C[Patient-reported internal state]
A --> D[Thinking and perception]
A --> E[Cognition and decision capacity signals]
B --> B1[Appearance behavior speech affect]
C --> C1[Mood]
D --> D1[Thought process content perception]
E --> E1[Cognition insight judgment]

See Fig 1. The classification step prevents a common exam error: choosing an answer that describes a real abnormality but assigns it to the wrong mental-status domain.

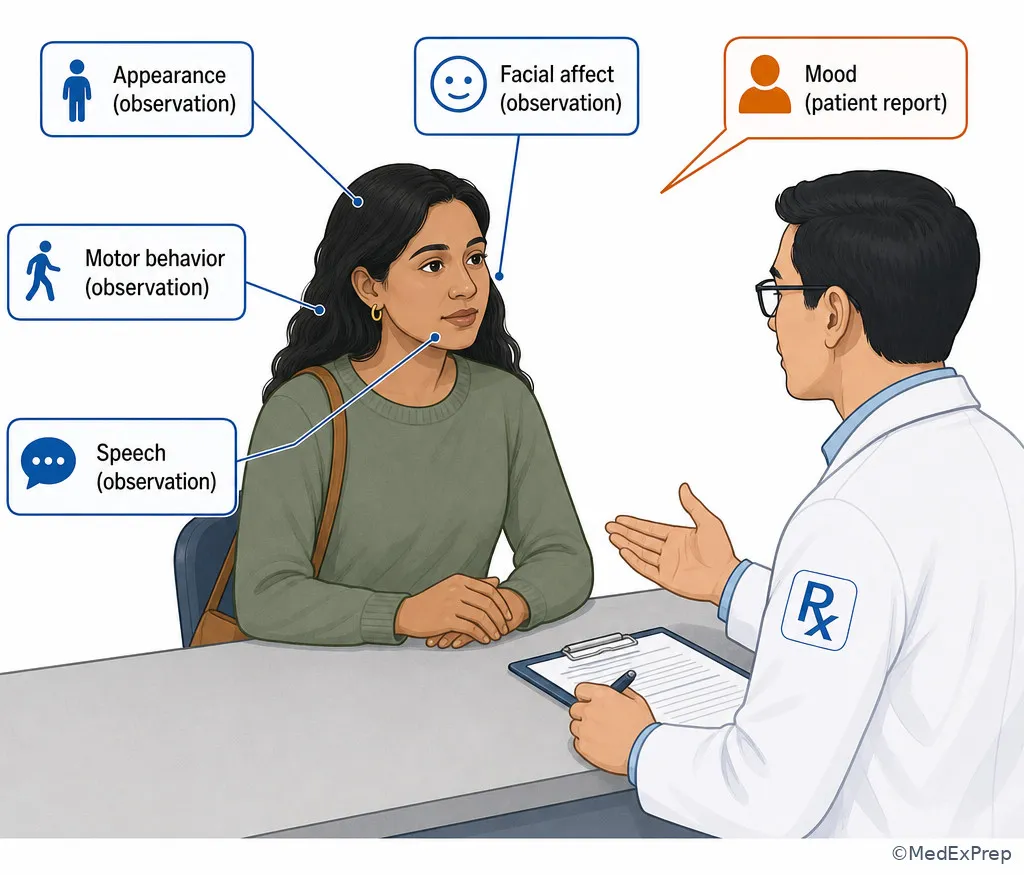
Observed versus reported findings
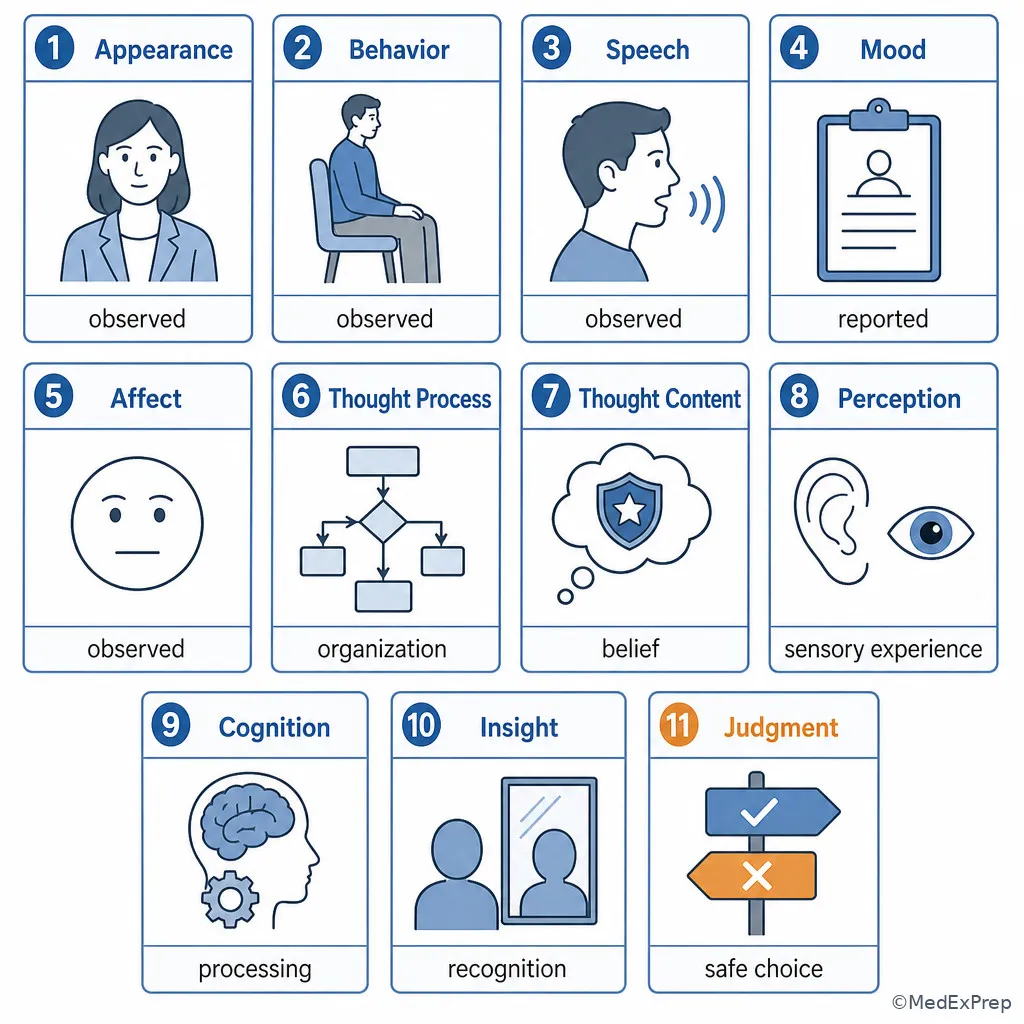
Exam takeaway: Appearance, behavior, speech, and affect are primarily observed, whereas mood is principally elicited from the patient's report.
Observed versus reported findings

Key Terms & Must-Know Facts

Key terms

Appearance
Observable features such as grooming, dress, and general presentation that can provide context for current functioning and medication tolerability.
Behavior
Observed interaction, motor activity, cooperation, agitation, slowing, or other actions during the encounter.
Speech
Observable characteristics of verbal output such as amount, rate, volume, and ease of interruption.
Mood
The patient's reported internal emotional state.
Affect
The clinician-observed expression and range of emotion during the encounter.
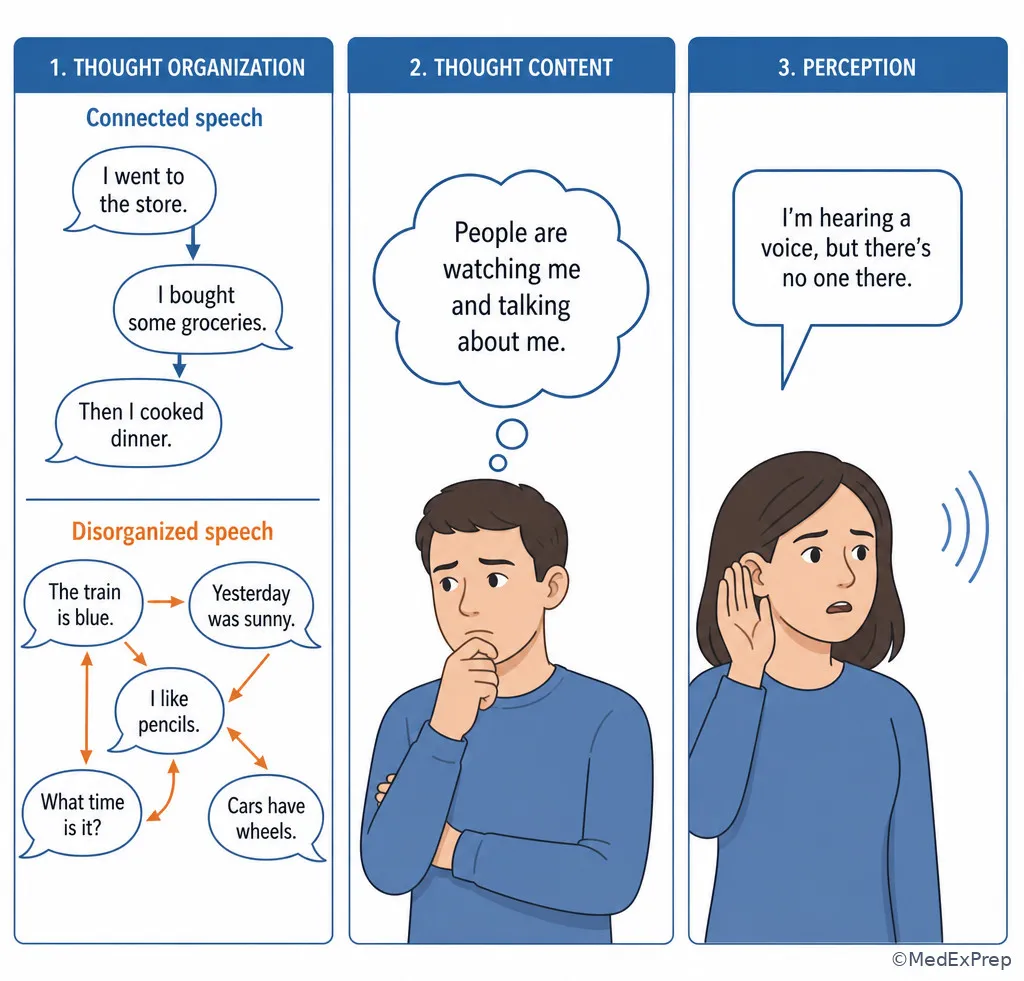
Thought process
How ideas are organized and connected.
Thought content
What the patient is thinking about, including beliefs, preoccupations, and safety-related content.
Perception
The patient's sensory experiences and possible perceptual disturbances.
Cognition
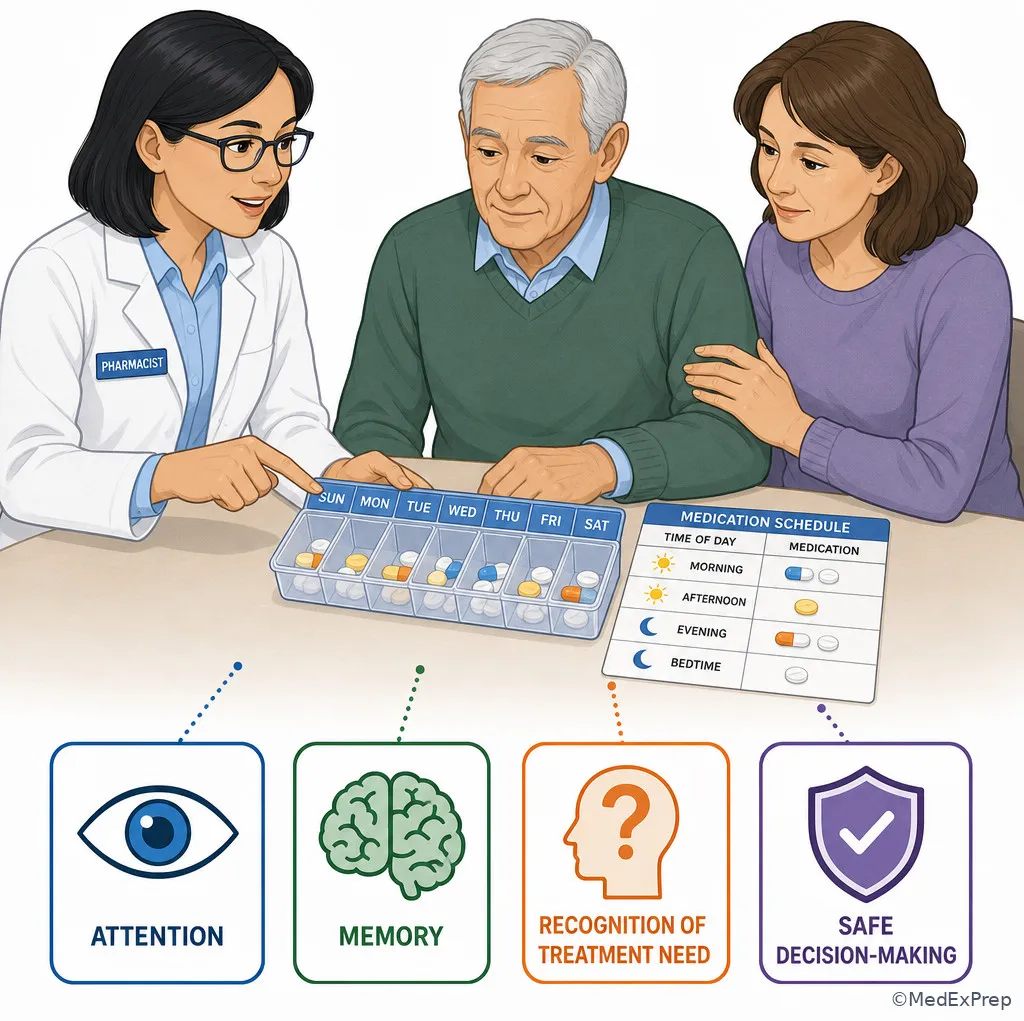
Current cognitive functioning relevant to attention, orientation, memory, and ability to participate meaningfully in medication-related decisions.
Insight
Degree to which the patient recognizes illness, symptoms, or the need for treatment.
Judgment
Ability to make safe, reality-based decisions in the circumstances presented.
Escalation
Communication or activation of the appropriate psychiatric, medical, emergency, or institutional response when a finding exceeds routine medication-management scope.

Must-know facts

  • The MSE describes the patient's current presentation; it does not replace longitudinal history.
  • Mood and affect are related but not interchangeable: mood is reported, affect is observed.
  • Thought process describes organization of thinking; thought content describes the subject matter of thinking.
  • Perceptual disturbance is classified separately from thought content even when the two occur together.
  • Cognitive change can be a medication-safety signal and should prompt review of drugs, substances, medical contributors, and recent changes.
  • Insight and judgment affect adherence, safe medication use, follow-up reliability, and the practicality of the care plan.
  • Medication-focused interpretation is central to pharmacist scope: ask whether the observed finding could reflect efficacy, adverse effect, withdrawal, intoxication, interaction, or nonadherence.
  • Urgent suicidality, homicidality, severe disorganization, dangerous behavior, or major alteration in mental status requires timely escalation to the appropriate team or emergency process.
  • Local crisis workflows differ; follow the institution's emergency and communication procedures.
Domain What the pharmacist is assessing Typical exam distinction Medication-relevant question
Appearance Observable general presentation What is seen, not what is inferred Could poor self-care, oversedation, or decline affect medication use?
Behavior Interaction and motor activity Agitation or slowing belongs here before assigning cause Could treatment, withdrawal, intoxication, or illness contribute?
Speech Rate, volume, amount, interruptibility Speech is observed output; thought process is organization of ideas Did a medication or clinical change coincide with the pattern?
Mood Patient-reported emotional state Subjective Is the target symptom improving or worsening?
Affect Observed emotional expression Objective observation Does observed expression match reported response and functioning?
Thought process Organization and connection of ideas How the patient thinks Is disorganization limiting safe participation in the medication plan?
Thought content Ideas, beliefs, preoccupations, safety content What the patient thinks about Is there self-harm, harm-to-others, or other dangerous content requiring escalation?
Perception Sensory experiences Perceiving versus believing Could symptoms be medication-, substance-, or illness-related?
Cognition Attention, orientation, memory, participation Ability to process information now Is medication administration or self-management safe?
Insight Recognition of illness and treatment need Understanding Will limited recognition undermine adherence?
Judgment Safety of decisions Decision quality Can the current medication plan be followed safely?

Core content

1. Appearance, behavior, speech, mood, and affect: classify before interpreting

A. Explanation

Decision conflict: A board question may give several observations and ask which one best describes the patient's emotional state or medication response. The conflict is whether to choose a subjective domain such as mood or an observed domain such as affect, behavior, or speech.

WHY THIS IS TESTED: Psychiatric pharmacy decisions often depend on separating what the patient reports from what the clinician observes. Conflating these domains can lead to incorrect interpretation of treatment response or adverse effects.

Start with the source of the information. If the patient says, 'I feel anxious and hopeless,' that is a report of mood. If the pharmacist observes minimal facial expression and little emotional variation, that is affect. If the patient is pacing and repeatedly stands up, that is behavior. If the patient's verbal output is unusually rapid or difficult to interrupt, classify the observation as speech before deciding what might be causing it. The MSE label describes the finding; medication causality requires a second step.

1. Ask whether the information is reported or observed.
2. If reported emotional state, classify as mood.
3. If visible emotional expression, classify as affect.
4. If motor/interpersonal action, classify as behavior.
5. If verbal-output characteristic, classify as speech.
6. Only then assess medication or safety significance.
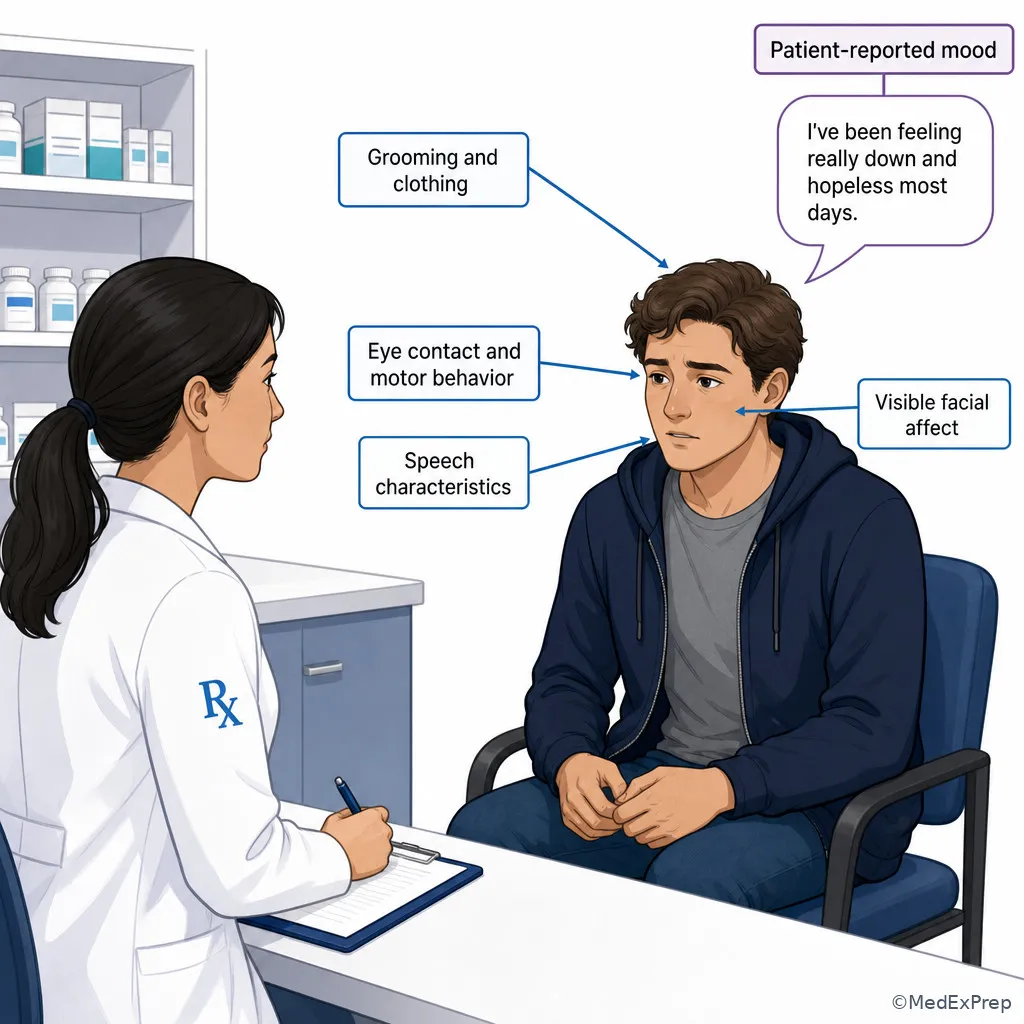
Fig 2. Observation zones in a pharmacist interview
Exam takeaway: Describe what is directly observed before assigning a medication-related explanation or psychiatric interpretation.
Fig 2. Observation zones in a pharmacist interview

See Fig 2. A strong exam answer remains descriptive before it becomes interpretive.

Reported versus observed emotional state
Exam takeaway: Mood comes from the patient's report; affect comes from the clinician's observation of emotional expression.
flowchart LR
A[Emotional information] --> B{Source?}
B -->|Patient report| C[Mood]
B -->|Observed expression| D[Affect]
C --> E[Compare with treatment target]
D --> E
E --> F[Assess concordance and medication relevance]

B. Worked example

Case: A 42-year-old patient with a history of depressive symptoms, hypertension, and migraine presents for medication follow-up. Serum sodium from last week is within the laboratory reference range. The patient states, 'My mood is much better,' but speaks softly, maintains little facial expression, and reports sleeping 7 hours nightly. A tempting clue is the normal laboratory value, which does not classify the MSE finding.

Identify the task: Determine which MSE domain is represented by limited visible emotional expression.
Extract key facts: Mood is verbally reported as improved; facial expression is observed as limited.
Apply the rule: Reported emotional state = mood; observed emotional expression = affect.
Eliminate: Speech describes the soft verbal output but does not classify the facial emotional expression. Cognition is not the target.
Verify: The correct domain is affect; medication significance should be interpreted with the rest of the history rather than inferred from the observation alone.

Most appropriate interpretation: Document the reported improvement in mood separately from the observed affective expression and assess whether the discrepancy is clinically meaningful for response, functioning, or tolerability.

C. Exam trap

Common wrong answer: mood. It is tempting because both mood and affect describe emotional state. Single eliminating clue: the finding is based on what the pharmacist observes rather than what the patient reports.

D. Checkpoint MCQ

A patient says, 'I feel calm today,' while showing little change in facial expression throughout the interview. Which MSE description most accurately classifies the observed facial finding?

  1. A. Mood
  2. B. Affect
  3. C. Thought content
  4. D. Judgment

Answer: B. Affect.

  • A. Mood: Tempting because the patient describes feeling calm, but mood is the reported internal state rather than the observed facial expression.
  • B. Affect: Correct because affect is the observed expression of emotion during the encounter.
  • C. Thought content: Tempting if the learner overgeneralizes all verbal or emotional material as cognition, but thought content concerns what the patient is thinking about.
  • D. Judgment: Tempting because behavior can reflect decision-making, but no decision-quality information is provided.
If you missed this: Review Appearance, behavior, speech, mood, and affect: classify before interpreting - focus on the reported mood versus observed affect distinction.

2. Thought process, thought content, and perception: separate organization, ideas, and sensory experience

A. Explanation

Decision conflict: A patient may present with unusual statements, disorganized communication, or sensory experiences. The testable conflict is whether the finding belongs to thought process, thought content, or perception.

WHY THIS IS TESTED: These domains can point to very different medication-safety and escalation concerns. A pharmacist must accurately describe what is occurring before considering medication effects, substance exposure, illness progression, or an urgent safety response.

Thought process asks, 'How are ideas organized?' Thought content asks, 'What ideas or beliefs occupy the patient's thinking?' Perception asks, 'Is the patient reporting a sensory experience that may not correspond to an external stimulus?' The exam may intentionally combine more than one abnormal domain in the same vignette; answer the specific finding named in the stem.

1. Identify the exact statement or observation being tested.
2. Organization of ideas -> thought process.
3. Belief, preoccupation, or safety idea -> thought content.
4. Sensory experience -> perception.
5. Screen for immediate danger.
6. Review medication, substance, and medical contributors.
Fig 3. Process-content-perception discriminator
Exam takeaway: Ask whether the stem describes how thoughts connect, what the patient believes, or what the patient senses.
graph TD
A[Unusual mental-status finding] --> B{Primary feature}
B -->|Organization of ideas| C[Thought process]
B -->|Belief preoccupation safety idea| D[Thought content]
B -->|Sensory experience| E[Perception]
C --> F[Assess ability to participate safely]
D --> G[Assess risk content]
E --> H[Assess safety and possible contributors]

See Fig 3. In a mixed case, classify first and then triage the safety implications.

Thought organization versus content versus perception
Exam takeaway: Three findings can coexist, but each should be documented in its own domain before medication-related interpretation.
Thought organization versus content versus perception

B. Worked example

Case: A 29-year-old patient with anxiety symptoms, asthma, and a remote ankle fracture presents after a recent medication change. Heart rate is 88 beats/min and oxygen saturation is normal. During the interview, the patient repeatedly shifts from medication costs to a neighbor, then to a television program without clear connections. The patient also states, 'I hear a voice telling me I am worthless.' The normal oxygen saturation is distracting, and the auditory report is a tempting clue if the question specifically asks about the disorganized sequence of ideas.

Identify the task: Classify the disconnected sequence of ideas.
Extract key facts: The defining feature is organization of ideas; a separate sensory experience is also present.
Apply the rule: Organization belongs to thought process.
Eliminate: Perception is relevant to the reported voice, but it does not answer the question about idea organization.
Verify safety: Because the voice has negative content, assess whether there is self-harm or command content and escalate if risk is present.

Most appropriate next step: Document the disorganized thought process and the perceptual report as separate findings, perform medication/substance review, and communicate urgent safety concerns if the content indicates risk.

C. Exam trap

Common wrong answer: perception. It is tempting because the vignette contains a reported voice. Single eliminating clue: the question asks about the way ideas are connected, which is thought process.

D. Checkpoint MCQ

Which finding is best classified as thought content rather than thought process or perception?

  1. A. The patient repeatedly changes topics without understandable connections.
  2. B. The patient reports hearing a voice when no speaker is present.
  3. C. The patient is preoccupied with a fixed belief that others intend harm.
  4. D. The patient answers in a very low-volume voice.

Answer: C.

  • A: Tempting because it involves thinking, but it describes organization and therefore thought process.
  • B: Tempting because it may coexist with abnormal beliefs, but it is a sensory experience and therefore perception.
  • C: Correct because the defining feature is the subject matter and belief occupying the patient's thinking.
  • D: Tempting because verbal output is part of the interview, but volume is a speech characteristic.
If you missed this: Review Thought process, thought content, and perception: separate organization, ideas, and sensory experience - focus on how versus what versus sensed.
Quick Recall:

  • Fill in the blank: Patient-reported emotional state = mood; observed emotional expression = affect.
  • True or false: A sensory experience and a belief about that experience are automatically the same MSE domain. False.
  • One-liner: 'How are the patient's ideas connected?' -> Thought process.

3. Cognition, insight, and judgment: connect mental status to medication safety

A. Explanation

Decision conflict: A patient may know where they are yet still be unable to follow a medication plan, may understand a diagnosis but make unsafe medication decisions, or may have impaired attention that changes the safety of counseling and self-administration. The conflict is deciding whether the key problem is cognition, insight, or judgment.

WHY THIS IS TESTED: Psychiatric pharmacists routinely determine whether a medication plan is understandable, feasible, and safe. These domains influence adherence assessment, caregiver involvement, monitoring intensity, communication strategy, and the need for urgent evaluation when mental status changes abruptly or substantially.

Cognition concerns the patient's present ability to attend, orient, remember, and process information. Insight concerns recognition of illness, symptoms, or treatment need. Judgment concerns the safety and appropriateness of decisions. These constructs can overlap, but a board question usually provides one discriminating clue.

1. Is the problem processing or retaining information? -> cognition.
2. Is the problem recognizing illness or treatment need? -> insight.
3. Is the problem making a safe choice? -> judgment.
4. Determine whether medication self-management is reliable.
5. Check for recent medication, substance, or medical changes.
6. Escalate major or acute alteration in mental status.
Cognition-insight-judgment decision map
Exam takeaway: Processing information, recognizing the problem, and choosing safely are related but distinct assessment targets.
flowchart TD
A[Medication plan concern] --> B{What is impaired?}
B -->|Attention memory orientation processing| C[Cognition]
B -->|Recognition of illness or treatment need| D[Insight]
B -->|Safety of decisions| E[Judgment]
C --> F[Assess ability to understand and self-manage]
D --> G[Assess adherence implications]
E --> H[Assess immediate safety implications]
Medication self-management safety screen
Exam takeaway: MSE findings become pharmacist-relevant when they affect understanding, adherence, or safe medication use.
Medication self-management safety screen

B. Worked example

Case: A 68-year-old patient with hypertension, chronic kidney disease, and a psychiatric medication regimen is seen after a transition of care. Blood pressure is 132/76 mm Hg. The patient correctly identifies the clinic and date, but cannot sustain attention long enough to review a three-drug regimen and repeatedly forgets instructions given minutes earlier. The normal blood pressure is distracting, and intact orientation is a tempting clue suggesting there is no cognitive problem.

Identify the task: Decide which MSE domain most directly threatens safe medication self-management.
Extract key facts: Orientation is intact, but attention and immediate retention are impaired.
Apply the rule: Attention and memory problems are cognitive findings.
Eliminate: Insight is not the primary issue because no evidence says the patient denies illness; judgment is not directly tested by a decision in the vignette.
Verify safety: Review medication and medical contributors, involve the appropriate team/caregiver if permitted, and avoid assuming the patient can independently execute a complex regimen.

Best pharmacist response: Treat the cognitive change as a medication-safety signal, reconcile the regimen, assess recent medication or substance changes and relevant clinical data, and communicate with the treatment team when the alteration is new, substantial, or potentially dangerous.

C. Exam trap

Common wrong answer: intact cognition because orientation is intact. It is tempting because orientation is a recognizable cognitive element. Single eliminating clue: the patient cannot sustain attention or retain instructions, so cognition is still impaired despite intact orientation.

D. Checkpoint MCQ

A patient states, 'There is nothing wrong with me, so I do not need these medications,' despite discussing repeated prior treatment episodes. Which domain is most directly demonstrated?

  1. A. Cognition
  2. B. Insight
  3. C. Perception
  4. D. Speech

Answer: B. Insight.

  • A. Cognition: Tempting because reasoning is involved, but no deficit in attention, orientation, or memory is described.
  • B. Insight: Correct because the key feature is lack of recognition of illness or treatment need.
  • C. Perception: Tempting if the learner interprets disagreement with treatment as altered reality testing, but no sensory experience is described.
  • D. Speech: Tempting because the finding is conveyed verbally, but the content reflects recognition rather than speech characteristics.
If you missed this: Review Cognition, insight, and judgment: connect mental status to medication safety - focus on processing versus recognition versus safe decision-making.

4. Integrating MSE findings with medication safety and escalation

A. Explanation

Decision conflict: Once an abnormal MSE finding is identified, the pharmacist must decide whether to continue routine medication optimization, investigate a medication-related cause, or escalate immediately because the presentation signals potential danger or a major change in mental status.

WHY THIS IS TESTED: The BCPP candidate is expected to think like an advanced psychiatric pharmacy clinician: identify medication-related problems, interpret patient-specific information, recommend monitoring or regimen optimization, communicate with the interprofessional team, and recognize when the situation requires emergency or prescriber-led evaluation beyond pharmacist scope.

The safest sequence is describe -> assess risk -> review contributors -> recommend/communicate -> verify follow-up. MSE abnormalities should never be attributed automatically to a psychiatric disorder. Medication adverse effects, withdrawal, intoxication, interactions, and medical conditions may cause or worsen psychiatric symptoms. Acute safety threats supersede routine medication counseling.

1. Describe the MSE finding objectively.
2. Screen for immediate self-harm, harm-to-others, severe disorganization, dangerous behavior, or marked cognitive change.
3. If urgent risk is present, activate the appropriate escalation pathway.
4. If stable, review medications, recent changes, adherence, substances, and relevant medical data.
5. Recommend medication optimization or monitoring within pharmacist scope.
6. Document findings, communication, and follow-up plan.
Fig 4. Safety escalation during psychiatric pharmacy assessment
Exam takeaway: Immediate danger or major mental-status deterioration takes priority over routine medication optimization.
Fig 4. Safety escalation during psychiatric pharmacy assessment

See Fig 4. The exam-relevant action is usually recognition and escalation, not independently determining legal disposition or providing emergency physician-level management.

Fig 5. Medication-safety interpretation of an abnormal MSE
Exam takeaway: After urgent danger is excluded, connect the MSE change to medications, substances, adherence, and medical contributors before recommending optimization.
graph TD
A[Abnormal MSE finding] --> B{Immediate danger or major deterioration?}
B -->|Yes| C[Escalate per local emergency pathway]
B -->|No| D[Review medications and recent changes]
D --> E[Assess adherence withdrawal intoxication interactions]
E --> F[Review relevant medical and monitoring data]
F --> G[Recommend medication or monitoring plan]
G --> H[Document and communicate follow-up]

See Fig 5. This is the core pharmacist reasoning sequence for integrating MSE findings into comprehensive medication management.

Medication contributors checklist
Exam takeaway: Do not assume an abnormal mental-status finding is caused by the underlying psychiatric disorder before reviewing the regimen and recent exposures.
Medication contributors checklist

B. Worked example

Case: A 36-year-old patient with a psychiatric disorder, type 2 diabetes, and seasonal allergies presents for routine medication counseling after a recent regimen change. A fasting glucose value is mildly above the target documented in the chart. During the visit, the patient becomes increasingly disorganized and states that a voice is instructing them to harm another person. The mildly elevated glucose is clinically relevant in the longer term but is distracting from the immediate task.

Identify the task: Choose the most appropriate next pharmacist action.
Extract key facts: Disorganization plus a perceptual report with harm-to-others content creates an immediate safety concern.
Apply the rule: Urgent safety takes priority over routine metabolic counseling or elective medication adjustment.
Eliminate: Do not continue a routine visit, independently make a legal disposition, or focus first on the glucose result.
Verify: Notify the appropriate psychiatric/emergency team and follow the local crisis protocol; medication review can occur as part of the urgent evaluation.

Most appropriate next step: Escalate immediately according to the clinical setting's emergency process while communicating the observed MSE findings and medication context.

C. Exam trap

Common wrong answer: adjust the psychiatric medication first. It is tempting because medication optimization is central to psychiatric pharmacy. Single eliminating clue: the patient reports harm-to-others command content, making immediate safety escalation the priority.

D. Checkpoint MCQ

During a medication follow-up, a patient develops a substantial new alteration in attention and behavior after several recent medication changes. No immediate self-harm or harm-to-others content is elicited. What is the best pharmacist-facing next step?

  1. A. Assume progression of the psychiatric disorder and recommend increasing the primary psychotropic.
  2. B. Review the medication timeline, adherence, substance exposure, and relevant medical data, then communicate concerns to the treatment team.
  3. C. Determine the formal psychiatric diagnosis independently before contacting the team.
  4. D. Ignore the change because no suicidal statement is present.

Answer: B.

  • A: Tempting because worsening symptoms may lead to intensification, but automatic attribution to the psychiatric disorder skips medication and medical contributors.
  • B: Correct because a new mental-status change warrants medication-focused assessment and interprofessional communication even without explicit self-harm content.
  • C: Tempting because diagnostic clarification matters, but independent unrestricted diagnosis is outside the pharmacist role described in the course profile.
  • D: Tempting because suicidality is a major red flag, but significant cognitive or behavioral change can itself be clinically urgent.
If you missed this: Review Integrating MSE findings with medication safety and escalation - focus on safety first, then medication/substance/medical contributor review.
Quick Recall:

  • Fill in the blank: Inability to sustain attention is primarily a cognition finding.
  • True or false: Lack of explicit suicidality means a new major mental-status change can be managed as routine. False.
  • One-liner: Immediate danger present -> escalate before routine medication optimization.
MSE-to-medication decision bridge
Exam takeaway: Classification answers what the finding is; clinical integration answers what the pharmacist should do about it.
flowchart LR
A[Classify MSE domain] --> B[Determine acuity]
B --> C[Identify safety implications]
C --> D[Review regimen substances and medical context]
D --> E[Recommend monitor optimize or escalate]
E --> F[Document and hand off]
Integrated psychiatric pharmacy assessment
Exam takeaway: The MSE should be interpreted together with the medication list, patient history, monitoring data, and current treatment response.
Integrated psychiatric pharmacy assessment

Exam Traps & Differentiators

Common traps and distractors

  • Mood instead of affect: Tempting because both concern emotion. Eliminating clue: the stem says the clinician observed the expression.
  • Thought content instead of thought process: Tempting because both involve thinking. Eliminating clue: the question asks how ideas are organized rather than what the patient believes.
  • Thought content instead of perception: Tempting because unusual beliefs and sensory experiences may coexist. Eliminating clue: the stem describes hearing, seeing, or another sensory experience.
  • Insight instead of judgment: Tempting because both relate to higher-level decision-making. Eliminating clue: recognition of illness points to insight; an unsafe choice points to judgment.
  • Normal orientation = normal cognition: Tempting because orientation is easy to test. Eliminating clue: impaired attention or memory can still demonstrate cognitive dysfunction.
  • Medication adjustment before escalation: Tempting because the candidate is a pharmacist. Eliminating clue: immediate danger or major deterioration changes the priority to urgent team activation.
Looks similar but isn't Feature 1 Feature 2 Single best discriminator
Emotion Mood Affect Reported versus observed
Thinking Thought process Thought content How ideas connect versus what ideas are present
Unusual experience Thought content Perception Belief/preoccupation versus sensory experience
Treatment participation Insight Cognition Recognition of illness versus ability to process information
Safety of decisions Insight Judgment Recognition versus action/choice
Clinical response Medication optimization Urgent escalation Stability versus immediate danger or major deterioration

If the stem says..., think...

  • 'Patient reports feeling...' -> mood.
  • 'Observed facial expression/range...' -> affect.
  • 'Ideas are difficult to follow or poorly connected...' -> thought process.
  • 'Preoccupied with a belief or safety idea...' -> thought content.
  • 'Hears, sees, or otherwise senses something...' -> perception.
  • 'Cannot attend, retain instructions, or orient appropriately...' -> cognition and medication-safety assessment.
Choose-versus-reject MSE classification
Exam takeaway: Use the single discriminating clue in the stem instead of choosing the broadest psychiatric-sounding answer.
graph TD
A[Stem clue] --> B{Observed emotional expression?}
B -->|Yes| C[Choose affect reject mood]
B -->|No| D{Organization of ideas?}
D -->|Yes| E[Choose thought process reject content]
D -->|No| F{Sensory experience?}
F -->|Yes| G[Choose perception reject thought content]
F -->|No| H[Use domain-specific clue]
REVIEW CONNECTION: Return to Integrating MSE findings with medication safety and escalation when a stem asks not only what the finding is, but what the pharmacist should do next.

Algorithm / Approach

Use this compact approach whenever a BCPP-style vignette gives one or more MSE findings.

1. Classify: Place the finding in the correct MSE domain.
2. Prioritize: Determine whether immediate danger, severe disorganization, or major cognitive/behavioral deterioration is present.
3. Escalate if needed: Activate the appropriate psychiatric, medical, or emergency pathway within local policy.
4. Investigate contributors: Review medications, recent regimen changes, adherence, withdrawal, substance exposure, interactions, and relevant medical data.
5. Optimize: Recommend monitoring, counseling, regimen modification, or follow-up within pharmacist scope.
6. Communicate: Document objective findings, recommendations, escalation, and follow-up responsibilities.
Fig 6. Board-style MSE action algorithm
Exam takeaway: Classify first, prioritize safety second, then investigate medication-related contributors and communicate the plan.
flowchart TD
A[Classify MSE finding] --> B{Immediate safety threat or major deterioration?}
B -->|Yes| C[Escalate per local protocol]
B -->|No| D[Review medication and exposure timeline]
D --> E[Assess adherence interactions substances medical factors]
E --> F[Recommend optimization and monitoring]
C --> G[Communicate and document]
F --> G

See Fig 6. This sequence keeps the candidate inside pharmacist scope while still prioritizing patient safety.

Step Exam question to ask yourself Common mistake
Classify What exact domain does the stem describe? Jumping straight to a diagnosis or drug change
Prioritize Is there immediate danger or major deterioration? Treating all findings as routine
Investigate Could medications, substances, withdrawal, interactions, or medical factors contribute? Assuming psychiatric illness is the only cause
Optimize What medication-focused action is appropriate within pharmacist scope? Overstepping into unrestricted diagnosis or legal disposition
Communicate Who needs to know, what was observed, and what follow-up is required? Failing to document or hand off a safety concern

Self-check quiz

Question 1

A 34-year-old patient states, 'I feel very anxious today.' The pharmacist observes a neutral facial expression with little visible emotional change. Which pairing is most accurate?

  1. A. Anxiety = affect; neutral expression = mood
  2. B. Anxiety = mood; neutral expression = affect
  3. C. Anxiety = thought content; neutral expression = behavior
  4. D. Anxiety = cognition; neutral expression = judgment

Question 2

A patient answers questions with a sequence of ideas that is difficult to follow because the connections between topics are unclear. Which MSE domain is most directly being described?

  1. A. Thought process
  2. B. Thought content
  3. C. Perception
  4. D. Insight

Question 3

A patient says, 'I hear a voice speaking to me even though no one else is in the room.' Which domain best classifies the reported experience?

  1. A. Speech
  2. B. Perception
  3. C. Thought process
  4. D. Judgment

Question 4

A 72-year-old patient with multiple medications becomes newly inattentive and cannot retain medication instructions for more than a few minutes. The patient remains oriented to place. What is the best pharmacist-facing response?

  1. A. Conclude cognition is normal because orientation is intact.
  2. B. Increase the primary psychotropic because the change must represent psychiatric relapse.
  3. C. Treat the finding as a cognitive medication-safety signal and review recent drugs, exposures, and relevant medical data.
  4. D. Defer all assessment because cognition is outside psychiatric pharmacy scope.

Question 5

During a routine medication visit, a patient reports a sensory experience directing them to harm another person. What is the most appropriate priority for the pharmacist?

  1. A. Complete the routine adherence interview before contacting anyone.
  2. B. Independently determine whether the patient should be involuntarily committed.
  3. C. Recommend an elective medication switch and schedule follow-up next month.
  4. D. Escalate immediately according to the clinical setting's psychiatric or emergency safety process.

Answer key & explanations

1. Answer: B

  • A: Tempting because anxiety can be visibly expressed, but the stem explicitly says the patient reports feeling anxious, making it mood; the facial expression is observed and therefore affect.
  • B: Correct. Mood is the patient's reported internal emotional state, while affect is the observed emotional expression.
  • C: Tempting because anxiety can become a preoccupation and facial expression is behaviorally visible, but those are not the best classifications of the exact clues given.
  • D: Tempting because anxiety can interfere with concentration and decision-making, but no cognitive or judgment deficit is described.
If you missed this: Review Appearance, behavior, speech, mood, and affect: classify before interpreting - focus on reported mood versus observed affect.

2. Answer: A

  • A: Correct because the clue concerns the organization and connections between ideas.
  • B: Tempting because the patient is expressing ideas, but thought content concerns what those ideas are about rather than how they connect.
  • C: Tempting because perceptual abnormalities may accompany disorganized presentations, but no sensory experience is described.
  • D: Tempting because poorly organized communication may affect treatment participation, but recognition of illness or treatment need is not the feature being tested.
If you missed this: Review Thought process, thought content, and perception: separate organization, ideas, and sensory experience - focus on organization of ideas as thought process.

3. Answer: B

  • A: Tempting because the experience is described verbally, but speech refers to characteristics of verbal output rather than the sensory experience itself.
  • B: Correct because the defining clue is a reported sensory experience.
  • C: Tempting because unusual experiences may disrupt thinking, but the stem does not describe organization of ideas.
  • D: Tempting because behavior in response to the experience may involve judgment, but no decision or action is described.
If you missed this: Review Thought process, thought content, and perception: separate organization, ideas, and sensory experience - focus on sensory experience as perception.

4. Answer: C

  • A: Tempting because orientation is a cognitive domain, but intact orientation does not negate deficits in attention or memory.
  • B: Tempting because worsening mental status can occur with psychiatric relapse, but automatically increasing therapy before evaluating medication, substance, and medical contributors is unsafe reasoning.
  • C: Correct because new impairment in attention and retention can threaten medication safety and should trigger medication-focused and clinical review with appropriate team communication.
  • D: Tempting because formal diagnostic evaluation may require other clinicians, but medication-related assessment of cognitive change is clearly within the pharmacist-facing scope described for this course.
If you missed this: Review Cognition, insight, and judgment: connect mental status to medication safety - focus on the fact that orientation alone does not establish intact cognition.

5. Answer: D

  • A: Tempting because adherence assessment is normally important, but routine questioning should not delay response to an immediate harm-related safety concern.
  • B: Tempting because legal disposition may ultimately be considered by the appropriate authorities or clinicians, but independently making that determination is outside the pharmacist role specified in the exam profile.
  • C: Tempting because medication changes may ultimately be needed, but an elective switch and delayed follow-up do not address the immediate risk.
  • D: Correct because a harm-to-others sensory command is an urgent safety concern requiring immediate escalation according to the setting's established emergency pathway.
If you missed this: Review Integrating MSE findings with medication safety and escalation - focus on urgent safety concerns taking priority over routine medication optimization.

Rapid review / cheat-sheet

  • Observed emotion -> affect, not mood.
  • Disconnected organization -> thought process, not thought content.
  • Belief or preoccupation -> thought content, not perception.
  • Sensory experience -> perception.
  • Attention or retention failure -> cognition can be impaired even when orientation is intact.
  • Failure to recognize illness/treatment need -> insight.
  • Unsafe decision -> judgment.
  • New MSE change after regimen change -> review medications, adherence, withdrawal, substances, interactions, and relevant medical factors.
  • Immediate danger -> escalate before routine optimization.
  • Pharmacist role -> describe, assess medication-related risk, recommend, monitor, communicate, document, and refer/escalate when required.
MSE rapid-review dashboard
Exam takeaway: Use one discriminating clue per domain to classify the finding before moving to medication and safety decisions.
MSE rapid-review dashboard

See also: Psychiatric History Components for longitudinal context; Screening And Monitoring Scales for structured symptom measurement; Suicide Risk Red Flags and Mental Health Crisis Presentations for expanded safety assessment; Adherence Barrier Assessment for translating insight, cognition, and practical barriers into a feasible medication plan.

Blueprint anchor recap

This lesson is anchored to the supplied BCPP Person-Centered Care blueprint, especially psychiatric interview and mental status examination, health and medication history, medication-related problems, medications/substances/diseases that may cause or worsen psychiatric symptoms, comprehensive medication management, documentation, and interprofessional escalation. The emphasis remains pharmacist-facing: classify findings, connect them to medication safety and treatment response, recommend monitoring or optimization, and escalate urgent concerns without assuming unrestricted diagnostic, legal, or emergency procedural authority.

References / further study

  • Board of Pharmacy Specialties. BCPP Examination Blueprint excerpt supplied in the MedExPrep course source pack.
  • MedExPrep BCPP course outline. Assessment Foundations - Psychiatric Assessment Elements.

Keep reading, free

Enter your email to read lesson 2 now.

Free. We may also email you about our programs. No spam, and you can ask us to remove your email at any time.

Liked it?

BCPP Prep Course (BCPP) has 84 lessons.

BPSPrep
Programs
For organizations
ContactLog inGet a free guide